
















Published online Oct 19, 2026. doi: 10.5498/wjp.124636
Revised: August 1, 2026
Accepted: August 28, 2026
Published online: October 19, 2026
Processing time: 112 Days and 16.7 Hours
To examine the structural heterogeneity of mental health literacy (MHL) among community residents from a person-centered perspective and to provide em
To identify latent profiles of MHL, characterize their features, and demographic predictors of profile membership among community residents in Nanchang.
A multistage stratified cluster random sampling method was used to recruit 2467 permanent residents aged 18 years and older in Nanchang. The short-form National Mental Health Literacy Questionnaire was administered to assess nine subdimensions across the domains of knowledge, attitudes, and behaviors. Latent profile analysis (LPA) was conducted to identify distinct MHL profiles. Analysis of variance was performed to compare differences in depression, anxiety, inso
The LPA revealed three profiles: The integrated high literacy group (56.02%), the literacy imbalanced group (21.44%), and the integrated low literacy group (22.54%). When the integrated high literacy group was used as the reference category, males [odds ratio (OR) = 2.125], individuals with a junior high school education or below (OR = 3.050-3.626), individuals with a monthly income of less than 3000 yuan (OR = 2.555), and individuals with unstable employment (OR = 3.640) were more likely to belong to the integrated low literacy group. Depression, anxiety, and insomnia levels were higher in both the integrated low literacy and literacy imbalanced groups than in the inte
MHL exhibited significant structural heterogeneity among community residents. Mental health knowledge may represent a key component of the protective effects of MHL. Thus, mental health education should involve a more targeted and population-specific intervention model.
Core Tip: Three mental health literacy profiles emerged among community residents: Integrated high literacy, integrated low literacy, and literacy imbalanced. Compared with the integrated high literacy group, the low and imbalanced literacy group exhibited more severe depression, anxiety, insomnia, and problematic social media use. Part-time workers, retirees, and individuals with low levels of education were at higher risk of belonging to the low or imbalanced literacy group.
- Citation: Cao SK, Xiao JJ, Xu SP, Xie WX, Chao XL, Sun Q, Liu CJ, Wu GJ, Liu QS, Wang XP, Hao W, Luo T. Latent profiles of mental health literacy among community residents in Nanchang, China. World J Psychiatry 2026; 16(10): 124636
- URL: https://www.wjgnet.com/2220-3206/full/v16/i10/124636.htm
- DOI: https://dx.doi.org/10.5498/wjp.124636
Mental health literacy (MHL) refers to the knowledge and beliefs that facilitate the recognition, management, and prevention of mental disorders. It encompasses key components of mental health promotion, including cognition, attitudes, and behaviors[1]. Since the introduction of this concept by Jorm et al[2], MHL has been considered a crucial determinant of mental health outcomes and a key predictor of help-seeking behavior and mental health service utilization. Globally, insufficient MHL remains prevalent and is associated with delayed help-seeking, worsening of symptoms, and the continuously growing burden of mental health disorders[2-4]. In China, the Healthy China Initiative (2019-2030) identifies improvement in residents’ mental health as a national goal[5].
Theoretically, MHL has evolved from a unidimensional knowledge-based perspective to a multidimensional systems perspective. Jorm et al[2] proposed that MHL comprises four interrelated domains-recognition, knowledge, attitudes, and help-seeking efficacy-and emphasized that the translation of knowledge into behavior is central to its protective role. Chen et al[6] operationalized MHL as a three-dimensional structure comprising knowledge, attitudes, and behaviors and reported only low-to-moderate correlations among these dimensions. Jiang et al[7] further conceptualized MHL as a dynamic system comprising three interrelated components: Knowledge, beliefs, and actions. Deficiencies in any one of these components may reduce the overall effectiveness of the system. Collectively, these theories suggest that residents’ MHL exhibits multiple underlying patterns or latent classes rather than simply following a high-, moderate-, or low-level distribution.
Previous studies have focused on measuring MHL at the population level and examining its influencing factors[8,9], making it difficult to capture structural heterogeneity within the population. Latent profile analysis (LPA) can identify unobserved subgroups on the basis of multiple continuous indicators and reveal their distinct configurations across the dimensions of knowledge, attitudes, and behaviors, thereby addressing the limitations of variable-centered approaches[10]. However, few studies, either in China or abroad, have directly performed LPA for the multidimensional classifi
A large body of evidence shows that MHL is significantly and negatively associated with depression, anxiety[11-13], insomnia[14,15], and problematic social media use[16,17]. MHL also buffers the relationship between social media addiction and psychological distress[18-20]. Therefore, examining differences in mental health indicators across profiles by using depression, anxiety, insomnia, and problematic social media use as criterion variables can provide evidence for the external validity of the classification.
After identifying different latent profiles, examining the demographic factors associated with individuals’ profile membership is of considerable public health significance for accurately identifying high-risk groups. Gender, age, edu
This study included permanent residents aged 18 years and above in Nanchang and used a multistage stratified cluster random sampling method. LPA was conducted on the basis of MHL dimension scores to identify subgroups. Depression, anxiety, insomnia, and problematic social media use were subsequently used as criterion variables to examine external differences across profiles, and major demographic variables were used to predict profile membership. This study aimed to answer three research questions: What latent profiles of MHL exist among community residents in Nanchang? What are the characteristics of each latent profile? Which factors can predict membership in different latent profiles?
This study included permanent residents aged 18 and above from Nanchang city (born before May 1, 2007; individuals who had resided in Nanchang city for a cumulative period of more than 6 months were considered permanent residents).
On the basis of the complex sampling design, the sample size estimation formula used was as follows:
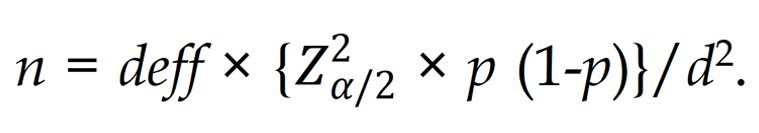
The design effect (deff) was set at 1.5, the confidence level α was 95% (two-sided), p was 20.0%, and the allowable error d was 2.0%. On the basis of these parameters, the calculated minimum sample size was 2306 individuals. Considering an estimated effective response rate of 85.0%, the planned sample size was rounded up to 2712 individuals.
This study was based on population data from the Seventh National Population Census of Nanchang and the most recent statistics issued by the Bureau of Statistics[21,22]. A multistage stratified cluster random sampling method was adopted. First, 3 districts/counties were selected proportionate to population size, followed by the selection of 9 streets/townships and 27 residential/village committees. Within each residential/village committee, 100 households were sys
Among the 2700 individuals approached, 2492 returned complete questionnaires, yielding a response rate of 92.30%. Following quality checking, 25 invalid questionnaires with incomplete responses or patterned answers were excluded, resulting in the inclusion of 2467 valid questionnaires in the final analysis. The valid response rate was 99.00%.
MHL: The Mental Health Literacy Questionnaire (MHLQ) was used to assess MHL[6]. This questionnaire consists of three dimensions: Mental health knowledge, attitudes, and behaviors. Mental health knowledge includes four subdimensions: Knowledge of mental health promotion, identification of mental disorders, etiology and risk factors, and treatment and rehabilitation of mental disorders. The instrument consists of 20 true-or-false items. A correct answer is assigned a score of 5 points, whereas an incorrect answer or a response of “don’t know” is assigned a score of 0 points. The total score ranges from 0 to 100. Mental health attitudes include two subdimensions, namely, mental health selfefficacy and mental health awareness, with a total of 8 items. A 4-point Likert scale is used, and the total score ranges from 8 to 32. Mental health behaviors are assessed through two specific case scenarios (depression and social anxiety disorder), covering several subdimensions, such as recognition of mental disorders, helpseeking behaviors for mental disorders, and behaviors toward individuals with mental disorders. In total, 3 dimensions and 8 items are present, with total scores ranging from 0 to 40. In this study, the subdimension scores were standardized as follows: (subdimension score/total score of that subdimension) × 100, converted to a standardized score ranging from 0 to 100[6]. In this study, the Cronbach’s α values for the three parts of the scale-knowledge, attitudes, and behaviors-were 0.836, 0.910, and 0.753, respectively.
Problematic social media use: Problematic social media use was measured using the six-item Bergen Social Media Addiction Scale[23], with higher scores indicating greater problematic use and a score of 24 used as the clinical cutoff for social media disorder[24]; the Cronbach’s α was 0.887.
Depression: Depressive symptoms were measured using the nine-item Patient Health Questionnaire-9[25], with total scores ranging from 0 to 27 and higher scores indicating more severe depressive symptoms; the Cronbach’s α was 0.950.
Anxiety: Anxiety symptoms were measured using the seven-item Generalized Anxiety Disorder Scale[26], with total scores ranging from 0 to 21 and higher scores indicating more severe anxiety symptoms; the Cronbach’s α was 0.957.
Insomnia: Insomnia symptoms were assessed using the seven-item Insomnia Severity Index[27,28], with total scores ranging from 0 to 28 and higher scores indicating greater insomnia severity; the Cronbach’s α in this study was 0.957.
Public stigma: Perceived public stigma was measured using the 12-item Perceived Devaluation Discrimination Scale developed by Link[29]; the Chinese version of this scale was cross-culturally adapted by Zuo and Ai[30]. Items were summed on a 4-point Likert scale, with higher scores indicating greater stigma. The Cronbach’s α was 0.884.
Analyses were conducted in R 4.5.2 using packages such as tidyverse and mclust, with the significance level set at α = 0.05. LPA was performed on the basis of the scores of the nine dimensions of MHL. Models with one to six profiles were fitted sequentially, and the optimal model was selected by considering Akaike information criterion (AIC), Bayesian information criterion (BIC), sample-size adjusted BIC (aBIC), entropy (≥ 0.80), bootstrap likelihood ratio test (BLRT) (P < 0.05), model parsimony, stability of the substantive patterns across adjacent solutions, theoretical interpretability, and the proportion of each class (≥ 5%). When models with additional profiles were mainly subdivided into existing profiles without producing a stable and substantively distinct configuration, the more parsimonious solution was preferred. One-way analysis of variance was used to compare differences in depression, anxiety, insomnia, and problematic social media use across profiles, followed by Tukey’s HSD test for post hoc comparisons. Multinomial logistic regression was then conducted with latent profile membership as the dependent variable. The integrated high literacy group was the primary reference outcome, with an additional comparison performed using the literacy imbalanced group as the reference. Demographic predictors were included in the model. Categorical variables were dummy-coded, continuous variables were Z-standardized, and odds ratios (ORs) with 95%CIs were reported.
All participants provided informed consent. The study procedures were conducted in accordance with the Declaration of Helsinki and were approved by the local ethics committee. The approval number was AF-SG-03-2.1-IIT.
LPA was conducted using the nine dimensions of MHL as indicators. After a comprehensive evaluation of the AIC, BIC, aBIC, entropy, BLRT, class proportions, and interpretability, the three-class model was retained (entropy = 0.974, with reasonable class proportions) (Table 1). Although the four- to six-class models yielded lower information criterion values, they merely split one of the groups into subgroups that differed only in degree, without producing any qualitatively new configurations. The four-class model showed a decrease in entropy to 0.955, indicating increased classification uncer

| Model | Log-likelihood | Parameters | AIC | BIC | aBIC | Entropy | BLRT |
| Class 1 | -31500.19 | 10 | 63020.38 | -63078.49 | 63046.72 | - | - |
| Class 2 | -25529.32 | 101 | 51260.65 | -51847.53 | 51526.63 | 0.975320 | P < 0.01 |
| Class 3 | -25744.39 | 146 | 51780.79 | -52629.16 | 52165.28 | 0.974046 | P < 0.01 |
| Class 4 | -25217.48 | 192 | 50818.96 | -51934.62 | 51324.59 | 0.955356 | P < 0.01 |
| Class 5 | -24305.16 | 238 | 49086.31 | -50469.27 | 49713.09 | 0.970967 | P < 0.01 |
| Class 6 | -23695.03 | 284 | 47958.05 | -49608.31 | 48705.97 | 0.973029 | P < 0.01 |
The distributions of gender, marital status, educational level, employment status, and income level differed significantly across the three profiles (all P < 0.001). The integrated low literacy group was mainly characterized by males (52.9%); individuals with lower level of education, including junior high school or below (12.4%) and senior high school or technical secondary school (26.1%); individuals with unstable employment, including part-time employment (12.9%) and unemployment (7.0%); and individuals with a dispersed income distribution. In contrast, the integrated high literacy group was predominantly characterized by females (60.9%); individuals with higher level of education, namely, a college degree or above (79.7%); individuals with full-time employment (74.0%); and individuals with middle-income levels. The literacy imbalanced group had the highest proportion of females (65.4%), married individuals (76.9%), and individuals with middle-income levels, with those earning 3000-6000 yuan accounting for the greatest proportion (42.5%). Although age and place of residence showed partially significant differences across the three profiles, the actual differences were relatively small (Table 2).
| Variable | Integrated high literacy group (n = 1382) | Integrated low literacy group (n = 556) | Literacy imbalanced group (n = 529) | Test statistic | P value |
| Age | 37.42 ± 11.85 | 37.50 ± 11.70 | 35.72 ± 12.02 | F = 4.385 | 0.0126 |
| Gender | χ2 = 43.210 | < 0.001 | |||
| Male | 541 (39.1) | 294 (52.9) | 183 (34.6) | ||
| Female | 841 (60.9) | 262 (47.1) | 346 (65.4) | ||
| Marital status | χ2 = 27.190 | < 0.001 | |||
| Married | 1007 (72.9) | 377 (67.8) | 407 (76.9) | ||
| Unmarried | 328 (23.7) | 136 (24.5) | 96 (18.1) | ||
| Divorced | 31 (2.2) | 32 (5.8) | 16 (3.0) | ||
| Widowed | 16 (1.2) | 11 (2.0) | 10 (1.9) | ||
| Educational level | χ2 = 109.220 | < 0.001 | |||
| Junior high school or below | 51 (3.7) | 69 (12.4) | 21 (4.0) | ||
| Senior high school or technical secondary school | 230 (16.6) | 145 (26.1) | 78 (14.7) | ||
| Junior college or bachelor’s degree | 1049 (75.9) | 312 (56.1) | 413 (78.1) | ||
| Master’s degree or above | 52 (3.8) | 30 (5.4) | 17 (3.2) | ||
| Employment status | χ2 = 70.247 | < 0.001 | |||
| Full-time employment | 1023 (74.0) | 361 (64.9) | 383 (72.4) | ||
| Part-time employment | 54 (3.9) | 72 (12.9) | 39 (7.4) | ||
| Unemployed | 56 (4.1) | 39 (7.0) | 13 (2.5) | ||
| Retired | 132 (9.6) | 50 (9.0) | 50 (9.5) | ||
| Student | 117 (8.5) | 34 (6.1) | 44 (8.3) | ||
| Place of residence | χ2 = 4.897 | 0.0864 | |||
| Urban area | 1163 (84.2) | 488 (87.8) | 442 (83.6) | ||
| Township | 219 (15.8) | 68 (12.2) | 87 (16.4) | ||
| Monthly income | χ2 = 77.012 | < 0.001 | |||
| < 3000 yuan | 273 (19.8) | 145 (26.1) | 113 (21.4) | ||
| 3000-6000 yuan | 442 (32) | 165 (29.7) | 225 (42.5) | ||
| 6000-9000 yuan | 478 (34.6) | 140 (25.2) | 148 (28) | ||
| 9000-12000 yuan | 134 (9.7) | 53 (9.5) | 29 (5.5) | ||
| > 12000 yuan | 55 (4.0) | 53 (9.5) | 14 (2.6) |
One-way analysis of variance revealed that the three profiles differed significantly in terms of problematic social media use, depression, anxiety, insomnia, and stigma scores (all P < 0.001). In terms of depression and anxiety scores, both the integrated low literacy group and the literacy imbalanced group scored significantly higher than the integrated high literacy group did, whereas the difference between the former two profiles was not statistically significant. Insomnia scores showed a stepwise pattern: The integrated low literacy group had the highest score (10.26 ± 7.74), followed by the literacy imbalanced group (9.40 ± 5.93) and the integrated high literacy group (4.38 ± 4.75), with significant differences observed between all the groups. With respect to problematic social media use, the literacy imbalanced group had the highest score (10.44 ± 5.14), followed by the integrated low literacy group (9.46 ± 6.52) and the integrated high literacy group (8.16 ± 5.45), with significant pairwise differences observed between groups (Table 3).
| Variable | Integrated high literacy group (n = 1382) | Integrated low literacy group (n = 556) | Literacy imbalanced group (n = 529) | F value | Post hoc comparisons |
| Problematic social media use | 8.16 ± 5.45 | 9.46 ± 6.52 | 10.44 ± 5.14 | 34.288 | 3 > 2 > 1 |
| PHQ-9 | 6.83 ± 7.12 | 13.52 ± 9.93 | 13.83 ± 7.78 | 223.387 | 2 approximately = 3 > 1 |
| GAD-7 | 4.93 ± 5.70 | 10.56 ± 7.91 | 10.38 ± 6.21 | 230.054 | 2 approximately = 3 > 1 |
| ISI | 4.38 ± 4.75 | 10.26 ± 7.74 | 9.40 ± 5.93 | 272.787 | 2 > 3 > 1 |
| Stigma | 28.00 ± 4.69 | 30.22 ± 2.49 | 29.20 ± 3.11 | 65.941 | 2 > 3 > 1 |
When the integrated high literacy group was used as the reference, the likelihood of belonging to the integrated low literacy group was found to be greater for males than for females (OR = 2.125, P < 0.001). Similarly, individuals with an education level of junior high school or below (OR = 3.050-3.626), parttime workers (OR = 3.640), and individuals with a monthly income of less than 3000 yuan (OR = 2.555) had significantly higher odds of belonging to the integrated low literacy group. The likelihood of belonging to the integrated low literacy group for township residents was also lower than that for urban residents (OR = 0.370). Among the factors predicting belonging to the literacy imbalance group, the likelihood was significantly greater for parttime workers (OR = 3.838), retired individuals (OR = 6.958), and individuals with a monthly income of less than 3,000 yuan (OR = 1.579). When the literacy imbalanced group was considered the reference group, males (OR = 1.900) and individuals with junior high school education or below (OR = 3.042-3.125) had a higher probability of belonging to the integrated low literacy group, whereas retired individuals (OR = 0.218) had a lower probability of belonging to the integrated low literacy group (Table 4).
| Integrated high literacy group | Literacy imbalanced group | ||||||||
| Integrated low literacy group | Literacy imbalanced group | Integrated low literacy group | |||||||
| B | OR | 95%CI | B | OR | 95%CI | B | OR | 95%CI | |
| Gender (male)1 | 0.754 | 2.125c | 1.612-2.802 | 0.063 | 1.065 | 0.814-1.393 | 0.642 | 1.900b | 1.386-2.605 |
| Educational level2 | |||||||||
| Senior high/technical secondary school | 0.445 | 1.56 | 0.910-2.675 | 0.226 | 1.254 | 0.663-2.37 | 0.153 | 1.166 | 0.613-2.215 |
| Junior college/bachelor’s degree | 1.288 | 3.626c | 2.136-6.155 | 0.014 | 1.014 | 0.547-1.88 | 1.112 | 3.042b | 1.623-5.701 |
| Master’s degree or above | 1.115 | 3.050b | 1.392-6.679 | -0.228 | 0.796 | 0.332-1.912 | 1.139 | 3.125a | 1.252-7.800 |
| Employment status3 | |||||||||
| Full-time employment | -0.410 | 0.664 | 0.355-1.241 | 1.018 | 2.768b | 1.38-5.55 | -0.922 | 0.398a | 0.19-0.831 |
| Part-time employment | 1.292 | 3.640c | 1.832-7.234 | 1.345 | 3.838b | 1.695-8.689 | -0.047 | 0.954 | 0.407-2.237 |
| Retired | 0.287 | 1.332 | 0.528-3.358 | 1.940 | 6.958c | 2.796-17.316 | -1.524 | 0.218b | 0.08-0.593 |
| Place of residence4 | |||||||||
| Township | -0.995 | 0.370c | 0.249-0.548 | -0.268 | 0.765 | 0.547-1.071 | -0.674 | 0.510b | 0.332-0.783 |
| Monthly income5 | |||||||||
| 6000–9000 yuan | 0.938 | 2.555c | 1.634-3.994 | 0.457 | 1.579a | 1.02-2.445 | 0.437 | 1.548 | 0.95-2.522 |
This study identified three latent profiles of MHL, namely, the integrated high (56.02%), literacy imbalanced (21.44%), and integrated low literacy (22.54%) groups, along with differences in mental health indicators and demographic pre
The three profiles support multidimensional dynamic systems theory[2,7]. The integrated high literacy group showed comprehensive and coordinated development across knowledge, attitudes, and behaviors; the low literacy group exhibited limited development across all the components, reflecting a systemic lack. The imbalanced group provides crucial evidence for understanding internal imbalances in MHL. Unlike the knowledge-behavior translation gap, where knowledge exists but attitudes lag[31], this subtype shows an attitudefirst pattern: Moderately positive attitudes and help-seeking behavior despite weak knowledge. This suggests that attitudes may be shaped by life experiences or social modeling, not solely by knowledge. Kutcher et al[31] reported that increased knowledge does not necessarily lead to improved attitudes. Our findings complement these findings in the opposite direction: Partial activation of attitudes does not imply that knowledge is sufficiently developed. This highlights the asynchronous development of literacy com
The differences in depression, anxiety, insomnia, and problematic social media use verified external validity. The high group scored lowest, which aligns with Jorm et al[2] synergy expectation that coordinated knowledge, attitude, and behavior yield the strongest protection. The low group scored highest on depression, anxiety, and insomnia, reflecting vulnerability from insufficient knowledge and negative attitudes, preventing help-seeking motivation and leading to maladaptive coping[11,12]. The imbalanced group, with low knowledge but moderate attitudes and behaviors, showed distress comparable to that of the low group, suggesting that knowledge plays a fundamental role in the observed pro
Gender, educational level, employment status, and income significantly predicted profile membership. Women were more likely to belong to the imbalanced group than the low group, suggesting that their relative advantages in attitudes and help-seeking willingness may prevent them from falling into a completely low-literacy state. However, insufficient knowledge keeps them imbalanced. Employment status had a particularly pronounced effect. Compared with full-time workers, part-time workers were more likely to belong to both the low and imbalanced groups, while retirees were more likely to belong to the imbalanced group. The economic pressure and role loss associated with unstable employment and retirement may interfere with knowledge-behavior translation. Township residents had a lower likelihood of belonging to the low group but a higher likelihood of belonging to the imbalanced group, suggesting that urban–rural differences are reflected in access to resources and the efficiency of literacy translation[9].
On the basis of heterogeneous profiles, mental health popularization should shift to a segmented, precise model. The high group (56.02%) can be transformed into peer volunteers to consolidate literacy and expand coverage. The imbalanced group (21.44%) needs focused knowledge supplementation, emphasizing the identification of common disorders and effective help-seeking behavior and guiding existing attitudes toward professional channels to avoid using social media for emotional escape. The low group (22.54%) requires systematic literacy intervention using non-text media (videos, comics) embedded in daily community scenarios to lower cognitive barriers while improving attitudes through recovery narratives. This strategy addresses both cognitive and attitudinal barriers. Priority targets include part-time workers, retirees, and individuals with low levels of education, with targeted popularization delivered through employment services and senior centers to maximize effectiveness under limited resources.
This study has several limitations. First, the cross-sectional design does not allow causal inference; future longitudinal studies are needed to verify temporal relationships. Second, the sample was drawn only from Nanchang, limiting the generalizability of the findings. Third, the profile labels need cross-validation in other samples.
Nanchang community residents exhibited three literacy profiles: High (56.02%), imbalanced (21.44%), and low (22.54%). The imbalanced group, characterized by “attitude first, knowledge weak,” had distress comparable to that of the low group and exhibited the most problematic social media use, suggesting that knowledge plays a central role in the observed protective association of MHL. Without adequate knowledge, positive attitudes may not correspond to lower distress and may coexist with maladaptive behaviors. Women, part-time workers, retirees, and individuals with low levels of education are especially vulnerable. Mental health popularization must shift to a targeted model: Transforming the high group into peer educators, providing knowledge supplementation and professional navigation for the imba
| 1. | Jorm AF, Korten AE, Jacomb PA, Christensen H, Rodgers B, Pollitt P. “Mental health literacy”: a survey of the public’s ability to recognise mental disorders and their beliefs about the effectiveness of treatment. Med J Aust. 1997;166:182-186. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 1247] [Cited by in RCA: 1340] [Article Influence: 46.2] [Reference Citation Analysis (0)] |
| 2. | Jorm AF. Mental health literacy: empowering the community to take action for better mental health. Am Psychol. 2012;67:231-243. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 732] [Cited by in RCA: 882] [Article Influence: 58.8] [Reference Citation Analysis (1)] |
| 3. | Clement S, Schauman O, Graham T, Maggioni F, Evans-Lacko S, Bezborodovs N, Morgan C, Rüsch N, Brown JS, Thornicroft G. What is the impact of mental health-related stigma on help-seeking? A systematic review of quantitative and qualitative studies. Psychol Med. 2015;45:11-27. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 1906] [Cited by in RCA: 1734] [Article Influence: 157.6] [Reference Citation Analysis (3)] |
| 4. | Whiteford HA, Degenhardt L, Rehm J, Baxter AJ, Ferrari AJ, Erskine HE, Charlson FJ, Norman RE, Flaxman AD, Johns N, Burstein R, Murray CJ, Vos T. Global burden of disease attributable to mental and substance use disorders: findings from the Global Burden of Disease Study 2010. Lancet. 2013;382:1575-1586. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 4857] [Cited by in RCA: 4047] [Article Influence: 311.3] [Reference Citation Analysis (3)] |
| 5. | National Health Commission of the People’s Republic of China. Healthy China Action (2019-2030). [cite 11 Aug 2026] Available from: https://www.nhc.gov.cn/guihuaxxs/c100133/201907/2a6ed52f1c264203b5351bdbbadd2da8.shtml. |
| 6. | Chen ZY, Wang YX, Guo F, Zhang J, Jiang L. Survey on Chinese national mental health literacy. In: Fu XL, Zhang K, editors. Report on national mental health development in China (2017-2018). Beijing: Social Sciences Academic Press, 2019: 220-263. |
| 7. | Jiang GR, Zhao CX, Wei H, Yu LX, Li DY, Lin XB, Ren ZH. [Mental health literacy: connotation, measurement and new framework]. Xinli Kexue. 2020;43:232-238. [DOI] [Full Text] |
| 8. | Furnham A, Swami V. Mental Health Literacy: A Review of What It Is and Why It Matters. Int Persp Psych. 2018;7:240-257. [DOI] [Full Text] |
| 9. | Jiang GR, Li DY, Ren ZH, Yan YP, Wu XC, Zhu X, Yu LX, Xia M, Li FL, Wei H, Zhang Y, Zhao CX, Zhang L. [The current situation and characteristics of national mental health literacy in China]. Xinli Xuebao. 2021;53:182-198. [RCA] [DOI] [Full Text] [Cited by in Crossref: 6] [Cited by in RCA: 24] [Article Influence: 4.8] [Reference Citation Analysis (0)] |
| 10. | Collins LM, Lanza ST. Latent Class and Latent Transition Analysis. Wiley Series in Probability and Statistics. John Wiley & Sons, 2009. [DOI] [Full Text] |
| 11. | Coles ME, Coleman SL. Barriers to treatment seeking for anxiety disorders: initial data on the role of mental health literacy. Depress Anxiety. 2010;27:63-71. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 130] [Cited by in RCA: 117] [Article Influence: 7.3] [Reference Citation Analysis (0)] |
| 12. | Lam LT. Mental health literacy and mental health status in adolescents: a population-based survey. Child Adoles Psychiat Ment Health. 2014;8:26. [RCA] [DOI] [Full Text] [Cited by in Crossref: 60] [Cited by in RCA: 84] [Article Influence: 7.0] [Reference Citation Analysis (0)] |
| 13. | Reavley NJ, Jorm AF. Recognition of mental disorders and beliefs about treatment and outcome: findings from an Australian national survey of mental health literacy and stigma. Aust N Z J Psychiatry. 2011;45:947-956. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 143] [Cited by in RCA: 161] [Article Influence: 10.7] [Reference Citation Analysis (0)] |
| 14. | Ebert DD, Berking M, Thiart H, Riper H, Laferton JAC, Cuijpers P, Sieland B, Lehr D. Restoring depleted resources: Efficacy and mechanisms of change of an internet-based unguided recovery training for better sleep and psychological detachment from work. Health Psychol. 2015;34S:1240-1251. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 86] [Cited by in RCA: 93] [Article Influence: 9.3] [Reference Citation Analysis (0)] |
| 15. | Horsch C, Lancee J, Beun RJ, Neerincx MA, Brinkman WP. Adherence to Technology-Mediated Insomnia Treatment: A Meta-Analysis, Interviews, and Focus Groups. J Med Internet Res. 2015;17:e214. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 42] [Cited by in RCA: 58] [Article Influence: 5.3] [Reference Citation Analysis (0)] |
| 16. | Griffiths MD. Social Networking Addiction: Emerging Themes and Issues. J Addict Res Ther. 2013;4:e118. [DOI] [Full Text] |
| 17. | Schønning V, Hjetland GJ, Aarø LE, Skogen JC. Social Media Use and Mental Health and Well-Being Among Adolescents - A Scoping Review. Front Psychol. 2020;11:1949. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 121] [Cited by in RCA: 110] [Article Influence: 18.3] [Reference Citation Analysis (0)] |
| 18. | Ding KR, Wang SB, Xu WQ, Lin LH, Liao DD, Chen HB, Tan WY, Huang JH, Hou CL, Jia FJ. Low mental health literacy and its association with depression, anxiety and poor sleep quality in Chinese elderly. Asia Pac Psychiatry. 2022;14:e12520. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 2] [Cited by in RCA: 37] [Article Influence: 9.3] [Reference Citation Analysis (0)] |
| 19. | Huang X, Wang X, Hu J, Xue Y, Wei Y, Wan Y, Song X, Wang R, Zhang B, Fang J, Zhang S. Inadequate Mental Health Literacy and Insufficient Physical Activity Potentially Increase the Risks of Anxiety and Depressive Symptoms in Chinese College Students. Front Psychiatry. 2021;12:753695. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 12] [Cited by in RCA: 32] [Article Influence: 6.4] [Reference Citation Analysis (0)] |
| 20. | Zhang Z, Wang M, Meng G, Qi Y, Wang L, Dong GH. Altered dynamic reconfiguration of brain functional networks during gaming and deprivation in individuals with internet gaming disorder. J Behav Addict. 2025;14:776-792. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in RCA: 2] [Reference Citation Analysis (0)] |
| 21. | Nanchang Municipal Bureau of Statistics. Communiqué on the seventh national population census of Nanchang City (No. 1). [cite 11 Aug 2026] Available from: https://tjj.nc.gov.cn/ncstjj/tjgb/202106/6b5338aadf78452f992fad80fc172e34.shtml. |
| 22. | Nanchang Municipal Bureau of Statistics. Nanchang statistical yearbook 2025. [cite 11 Aug 2026] Available from: https://tjj.nc.gov.cn/ncstjj/nj/2025/mobile/index.html. |
| 23. | Schou Andreassen C, Billieux J, Griffiths MD, Kuss DJ, Demetrovics Z, Mazzoni E, Pallesen S. The relationship between addictive use of social media and video games and symptoms of psychiatric disorders: A large-scale cross-sectional study. Psychol Addict Behav. 2016;30:252-262. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 1508] [Cited by in RCA: 949] [Article Influence: 94.9] [Reference Citation Analysis (0)] |
| 24. | Luo T, Qin L, Cheng L, Wang S, Zhu Z, Xu J, Chen H, Liu Q, Hu M, Tong J, Hao W, Wei B, Liao Y. Determination the cut-off point for the Bergen social media addiction (BSMAS): Diagnostic contribution of the six criteria of the components model of addiction for social media disorder. J Behav Addict. 2021;10:281-290. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 32] [Cited by in RCA: 96] [Article Influence: 19.2] [Reference Citation Analysis (0)] |
| 25. | Kroenke K, Spitzer RL, Williams JB. The PHQ-9: validity of a brief depression severity measure. J Gen Intern Med. 2001;16:606-613. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 37319] [Cited by in RCA: 33160] [Article Influence: 1326.4] [Reference Citation Analysis (9)] |
| 26. | Spitzer RL, Kroenke K, Williams JB, Löwe B. A brief measure for assessing generalized anxiety disorder: the GAD-7. Arch Intern Med. 2006;166:1092-1097. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 26995] [Cited by in RCA: 22510] [Article Influence: 1125.5] [Reference Citation Analysis (23)] |
| 27. | Morin CM, Belleville G, Bélanger L, Ivers H. The Insomnia Severity Index: psychometric indicators to detect insomnia cases and evaluate treatment response. Sleep. 2011;34:601-608. [RCA] [PubMed] [DOI] [Full Text] [Full Text (PDF)] [Cited by in Crossref: 3953] [Cited by in RCA: 3557] [Article Influence: 237.1] [Reference Citation Analysis (4)] |
| 28. | Bai CJ, Ji DH, Chen LX, Li L, Wang CX. [Reliability and validity of Insomnia Severity Index in clinical insomnia patients]. Zhonguo Shiyong Huli Zazhi. 2018;34:2182-2186. |
| 29. | Link BG. Understanding Labeling Effects in the Area of Mental Disorders: An Assessment of the Effects of Expectations of Rejection. Am Soc Rev. 1987;52:96. [DOI] [Full Text] |
| 30. | Zuo B, Ai CG. [Relationship among group identification, self-esteem, and mental illness stigma]. Yingyong Xinlixue. 2011;17:299-303. |
| 31. | Kutcher S, Wei Y, Coniglio C. Mental Health Literacy: Past, Present, and Future. Can J Psychiatry. 2016;61:154-158. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 295] [Cited by in RCA: 437] [Article Influence: 43.7] [Reference Citation Analysis (0)] |
| 32. | Cooper S. Research on help-seeking for mental illness in Africa: Dominant approaches and possible alternatives. Transcult Psychiatry. 2016;53:696-718. [RCA] [PubMed] [DOI] [Full Text] [Cited by in Crossref: 25] [Cited by in RCA: 25] [Article Influence: 2.5] [Reference Citation Analysis (0)] |