
















Copyright: ©Author(s) 2026.
World J Psychiatry. Nov 19, 2026; 16(11): 125256
Published online Nov 19, 2026. doi: 10.5498/wjp.125256
Published online Nov 19, 2026. doi: 10.5498/wjp.125256
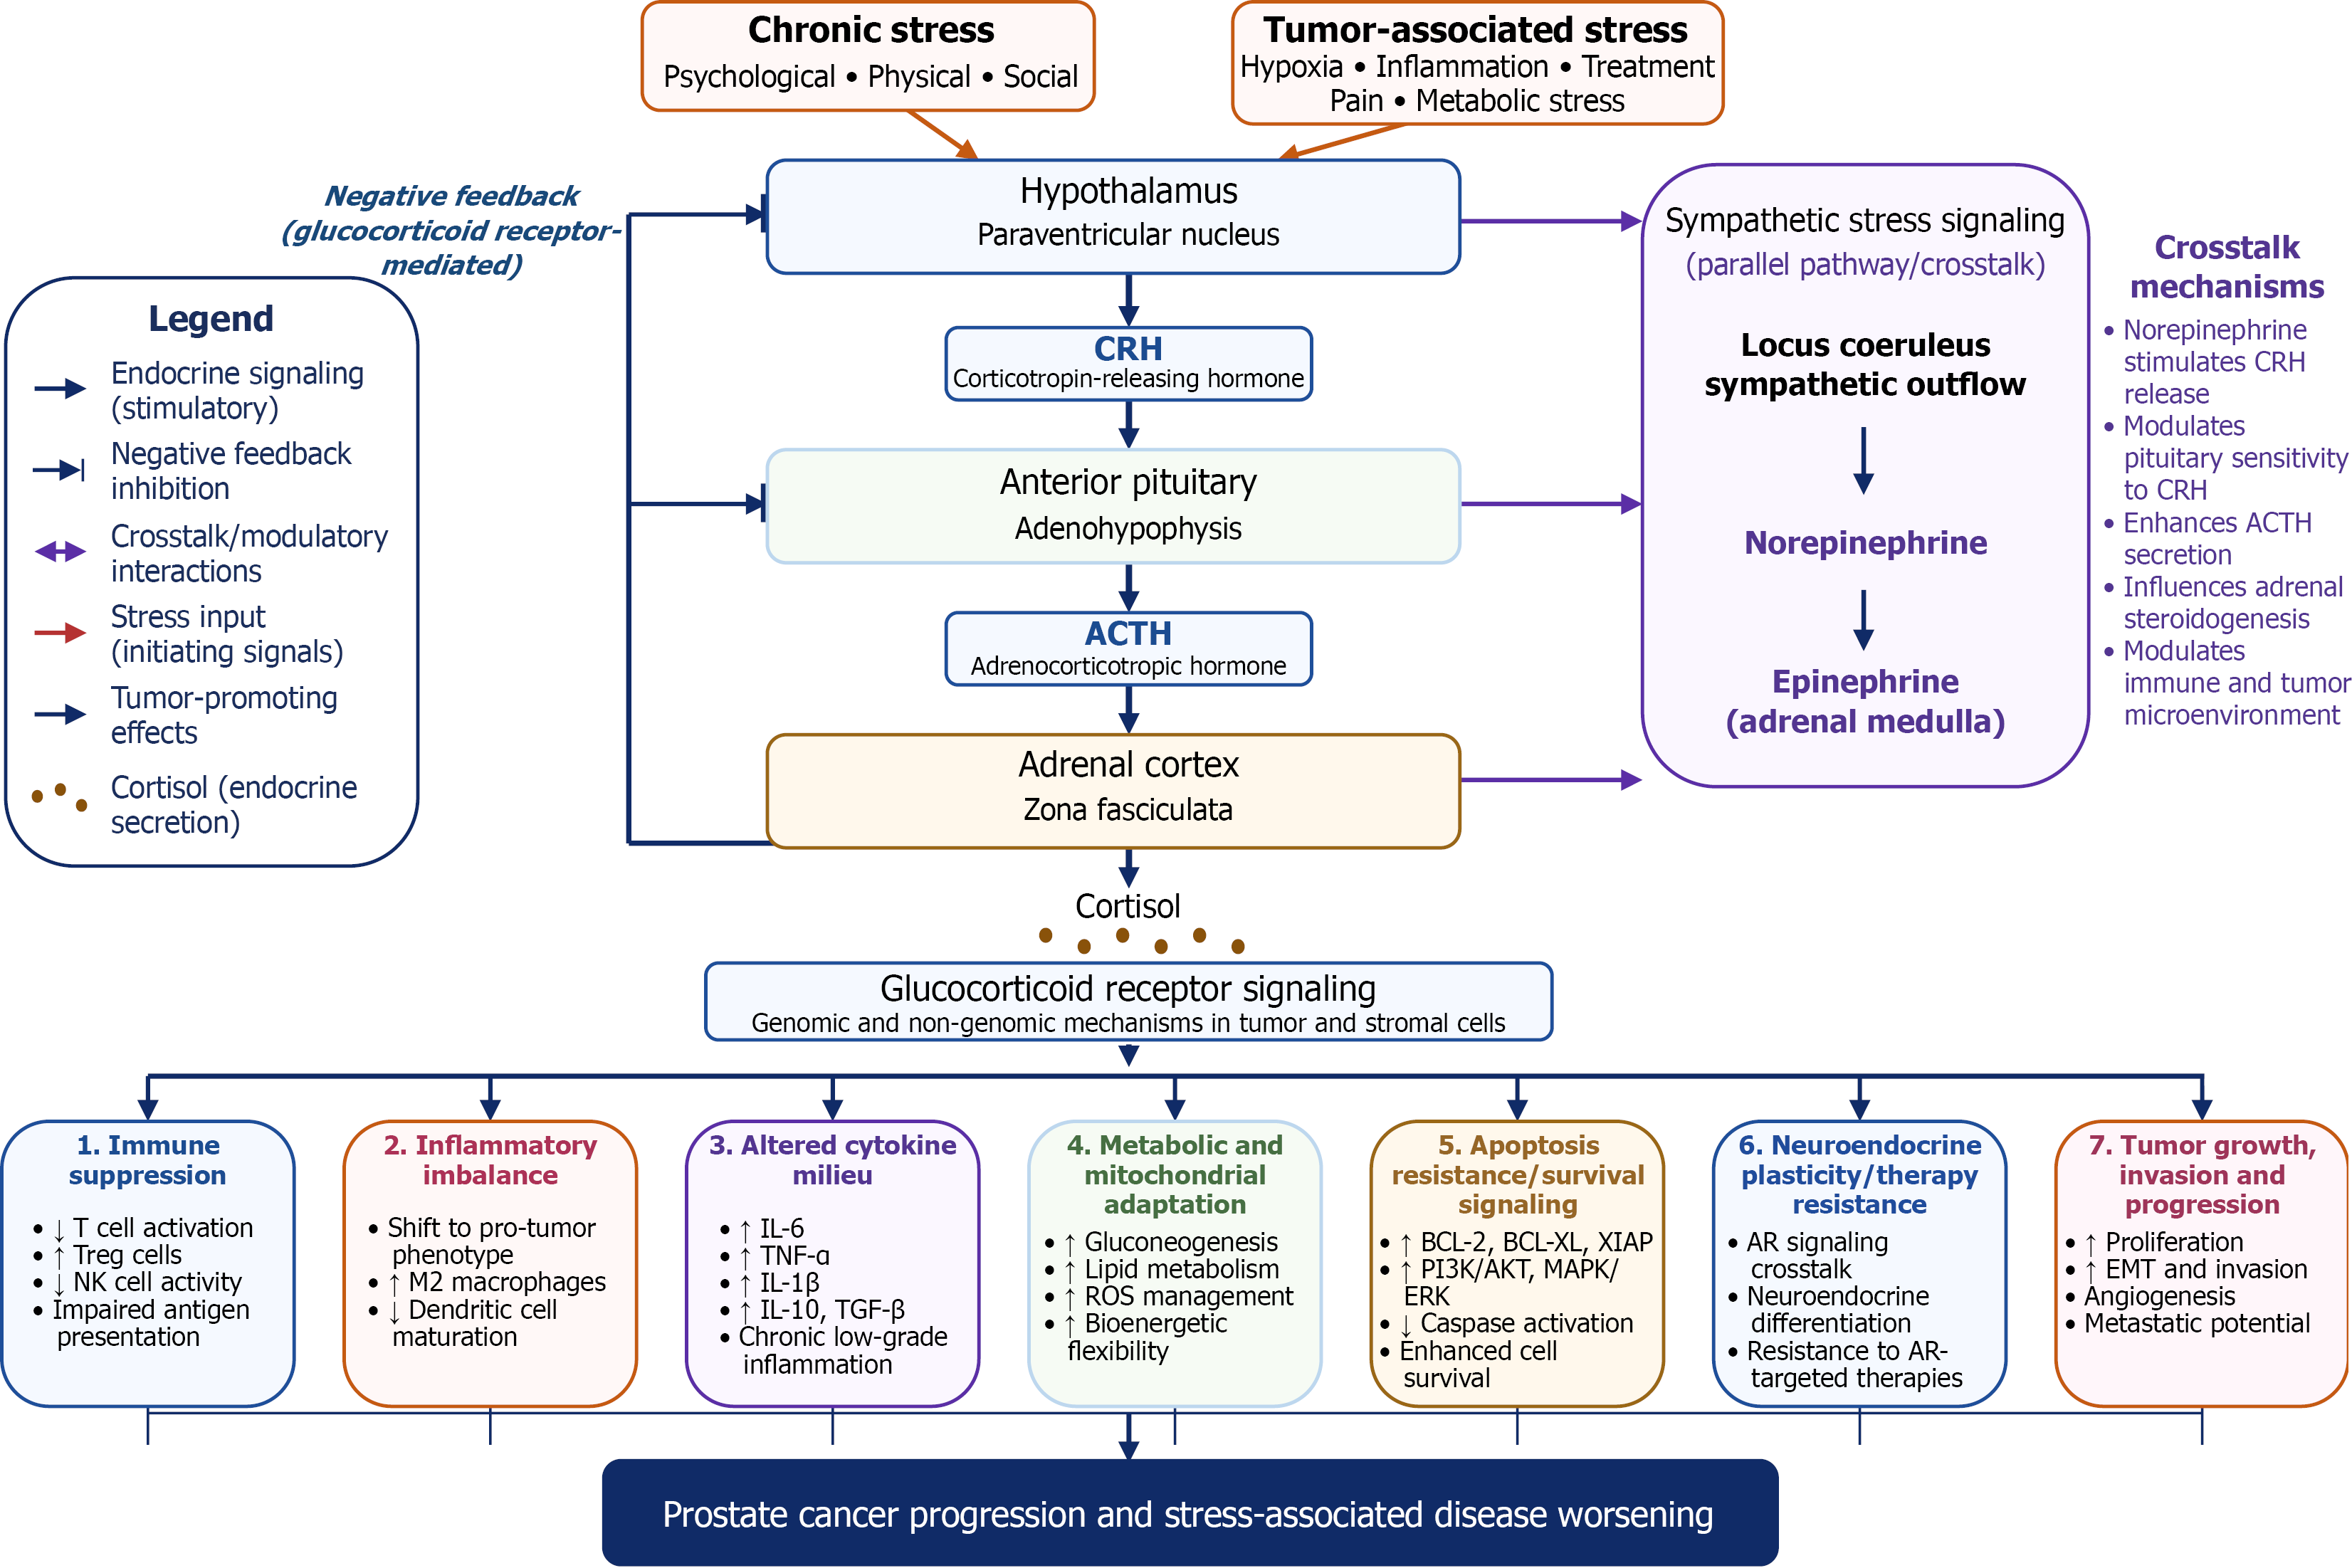
Figure 1 Represents hypothalamic-pituitary-adrenal axis and sympathetic signalling in the context of prostate cancer cellular processes.
Author-assembled schematic integrating hypothalamic-pituitary-adrenal axis activation, sympathetic/adrenergic signaling, cortisol-glucocorticoid receptor signaling and downstream prostate cancer (PCa)-associated responses. Direct evidence from PCa patients includes altered stress/cortisol profiles[18], associations of circulating interleukin-6 and tumor necrosis factor-α with disease extent and progression[73] and clinical evidence linking glucocorticoid receptor expression/signaling with antiandrogen resistance[74-76]. PCa preclinical/cellular evidence supports stress-induced β-adrenergic signaling, tumor growth, migration, and dissemination[13,77,78]. Asterisks indicate downstream links that have not been established as causal pathways in PCa patients and are supported predominantly by PCa cellular/preclinical studies or broader mechanistic cancer literature. CRH: Corticotropin releasing hormone; ACTH: Adrenocorticotropic hormone; NK: Natural killer; IL: Interleukin; TNF-α: Tumor necrosis factor alpha; TGF: Transforming growth factor; ROS: Reactive oxygen species; AR: Androgen receptor; EMT: Epithelial-mesenchymal transition.
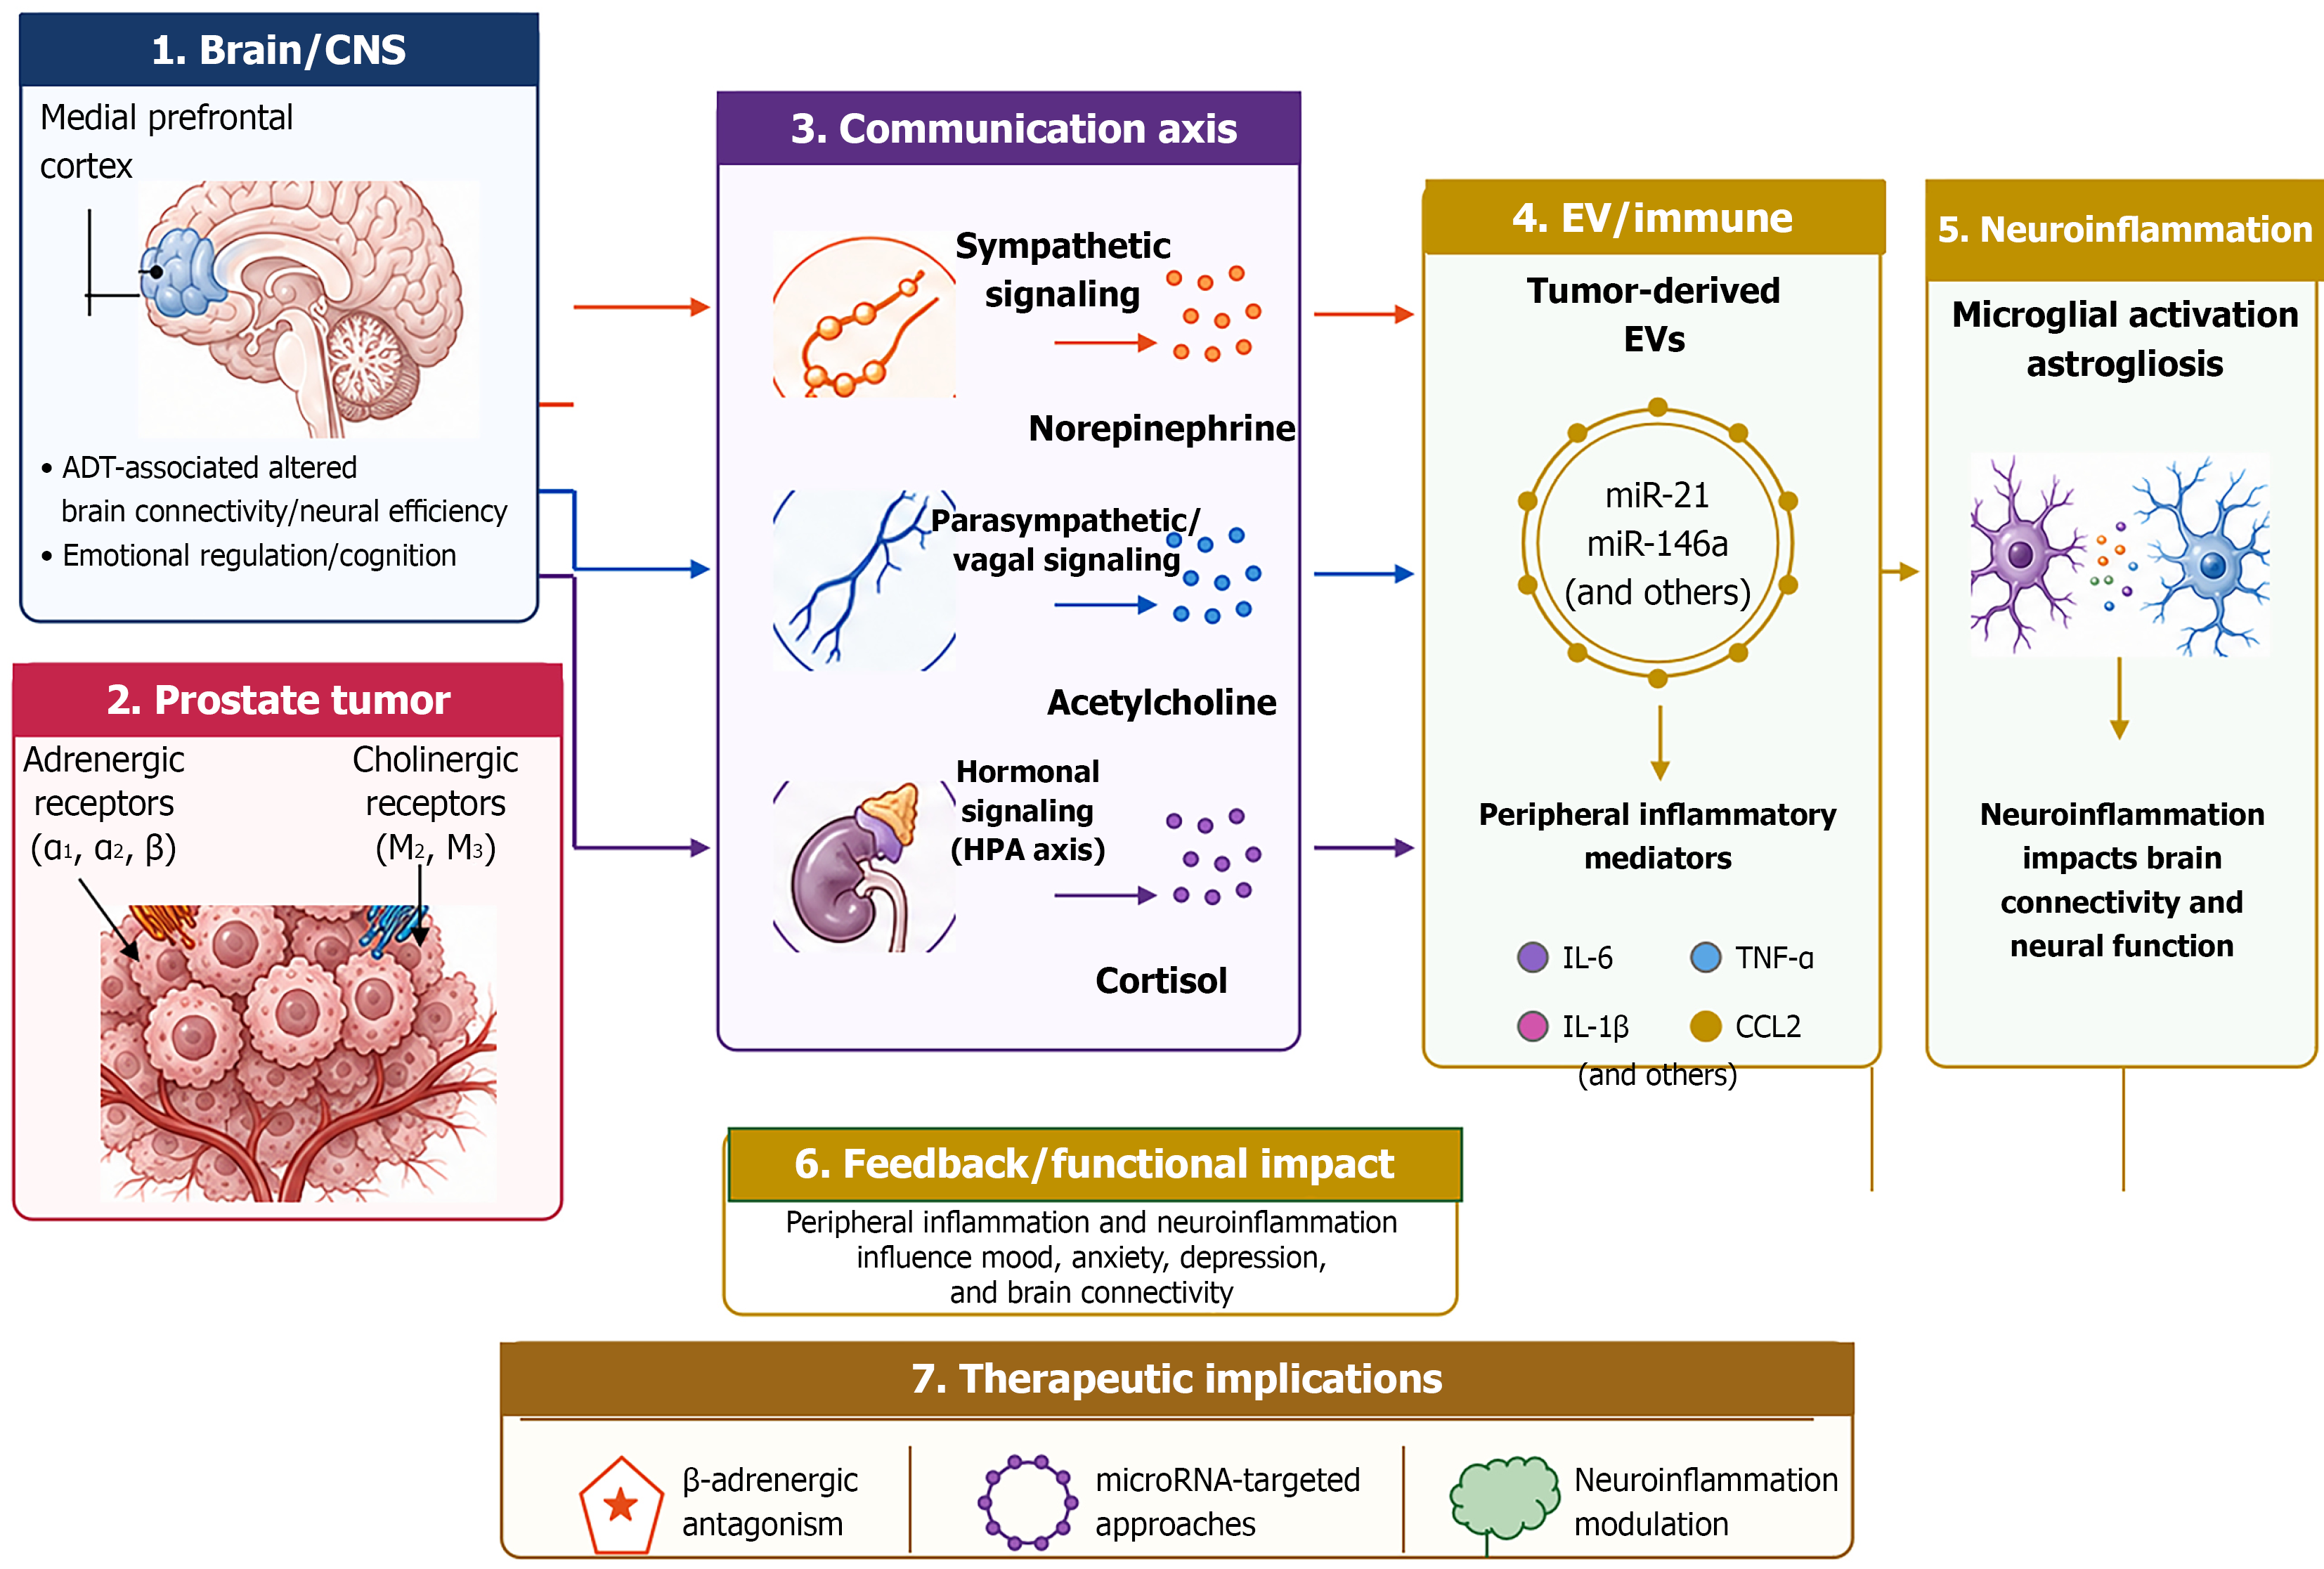
Figure 2 Depicts the brain-tumor communication through autonomic, hormonal, extracellular-vesicle, and inflammatory signaling in pro
- Citation: Bhave S, Darji Y, Prajapati A. Neuropsychiatric manifestations of prostate cancer and its treatment: Biological mechanisms and psycho-oncology perspectives. World J Psychiatry 2026; 16(11): 125256
- URL: https://www.wjgnet.com/2220-3206/full/v16/i11/125256.htm
- DOI: https://dx.doi.org/10.5498/wjp.125256