
















Copyright: ©Author(s) 2026.
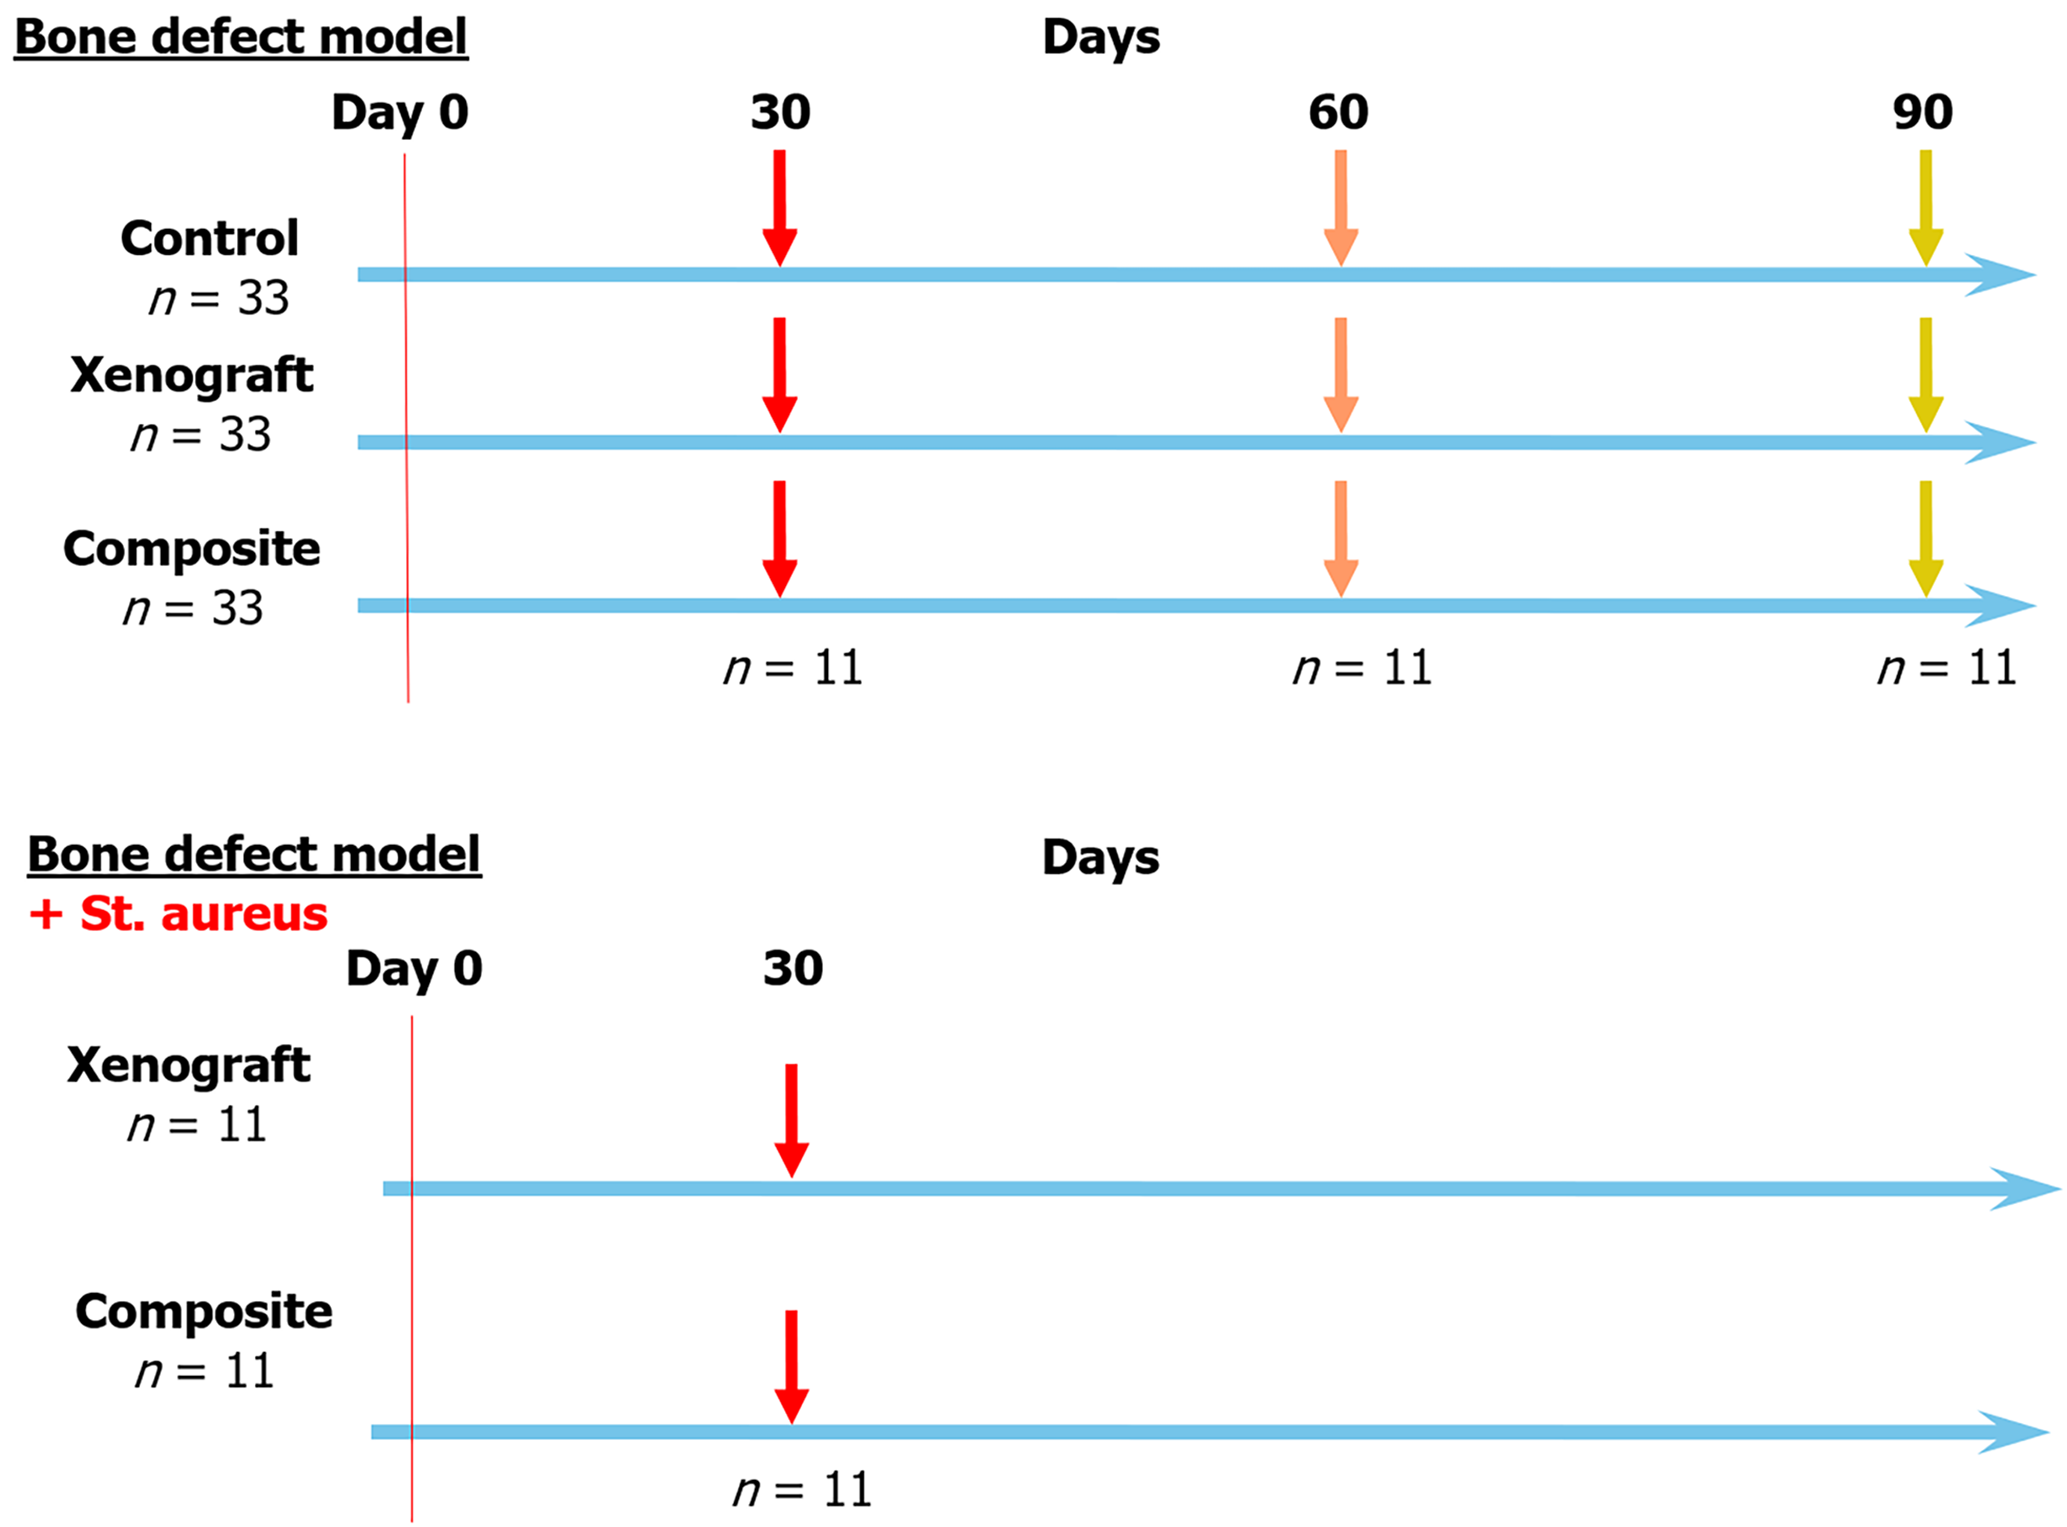
Figure 1
Study design.
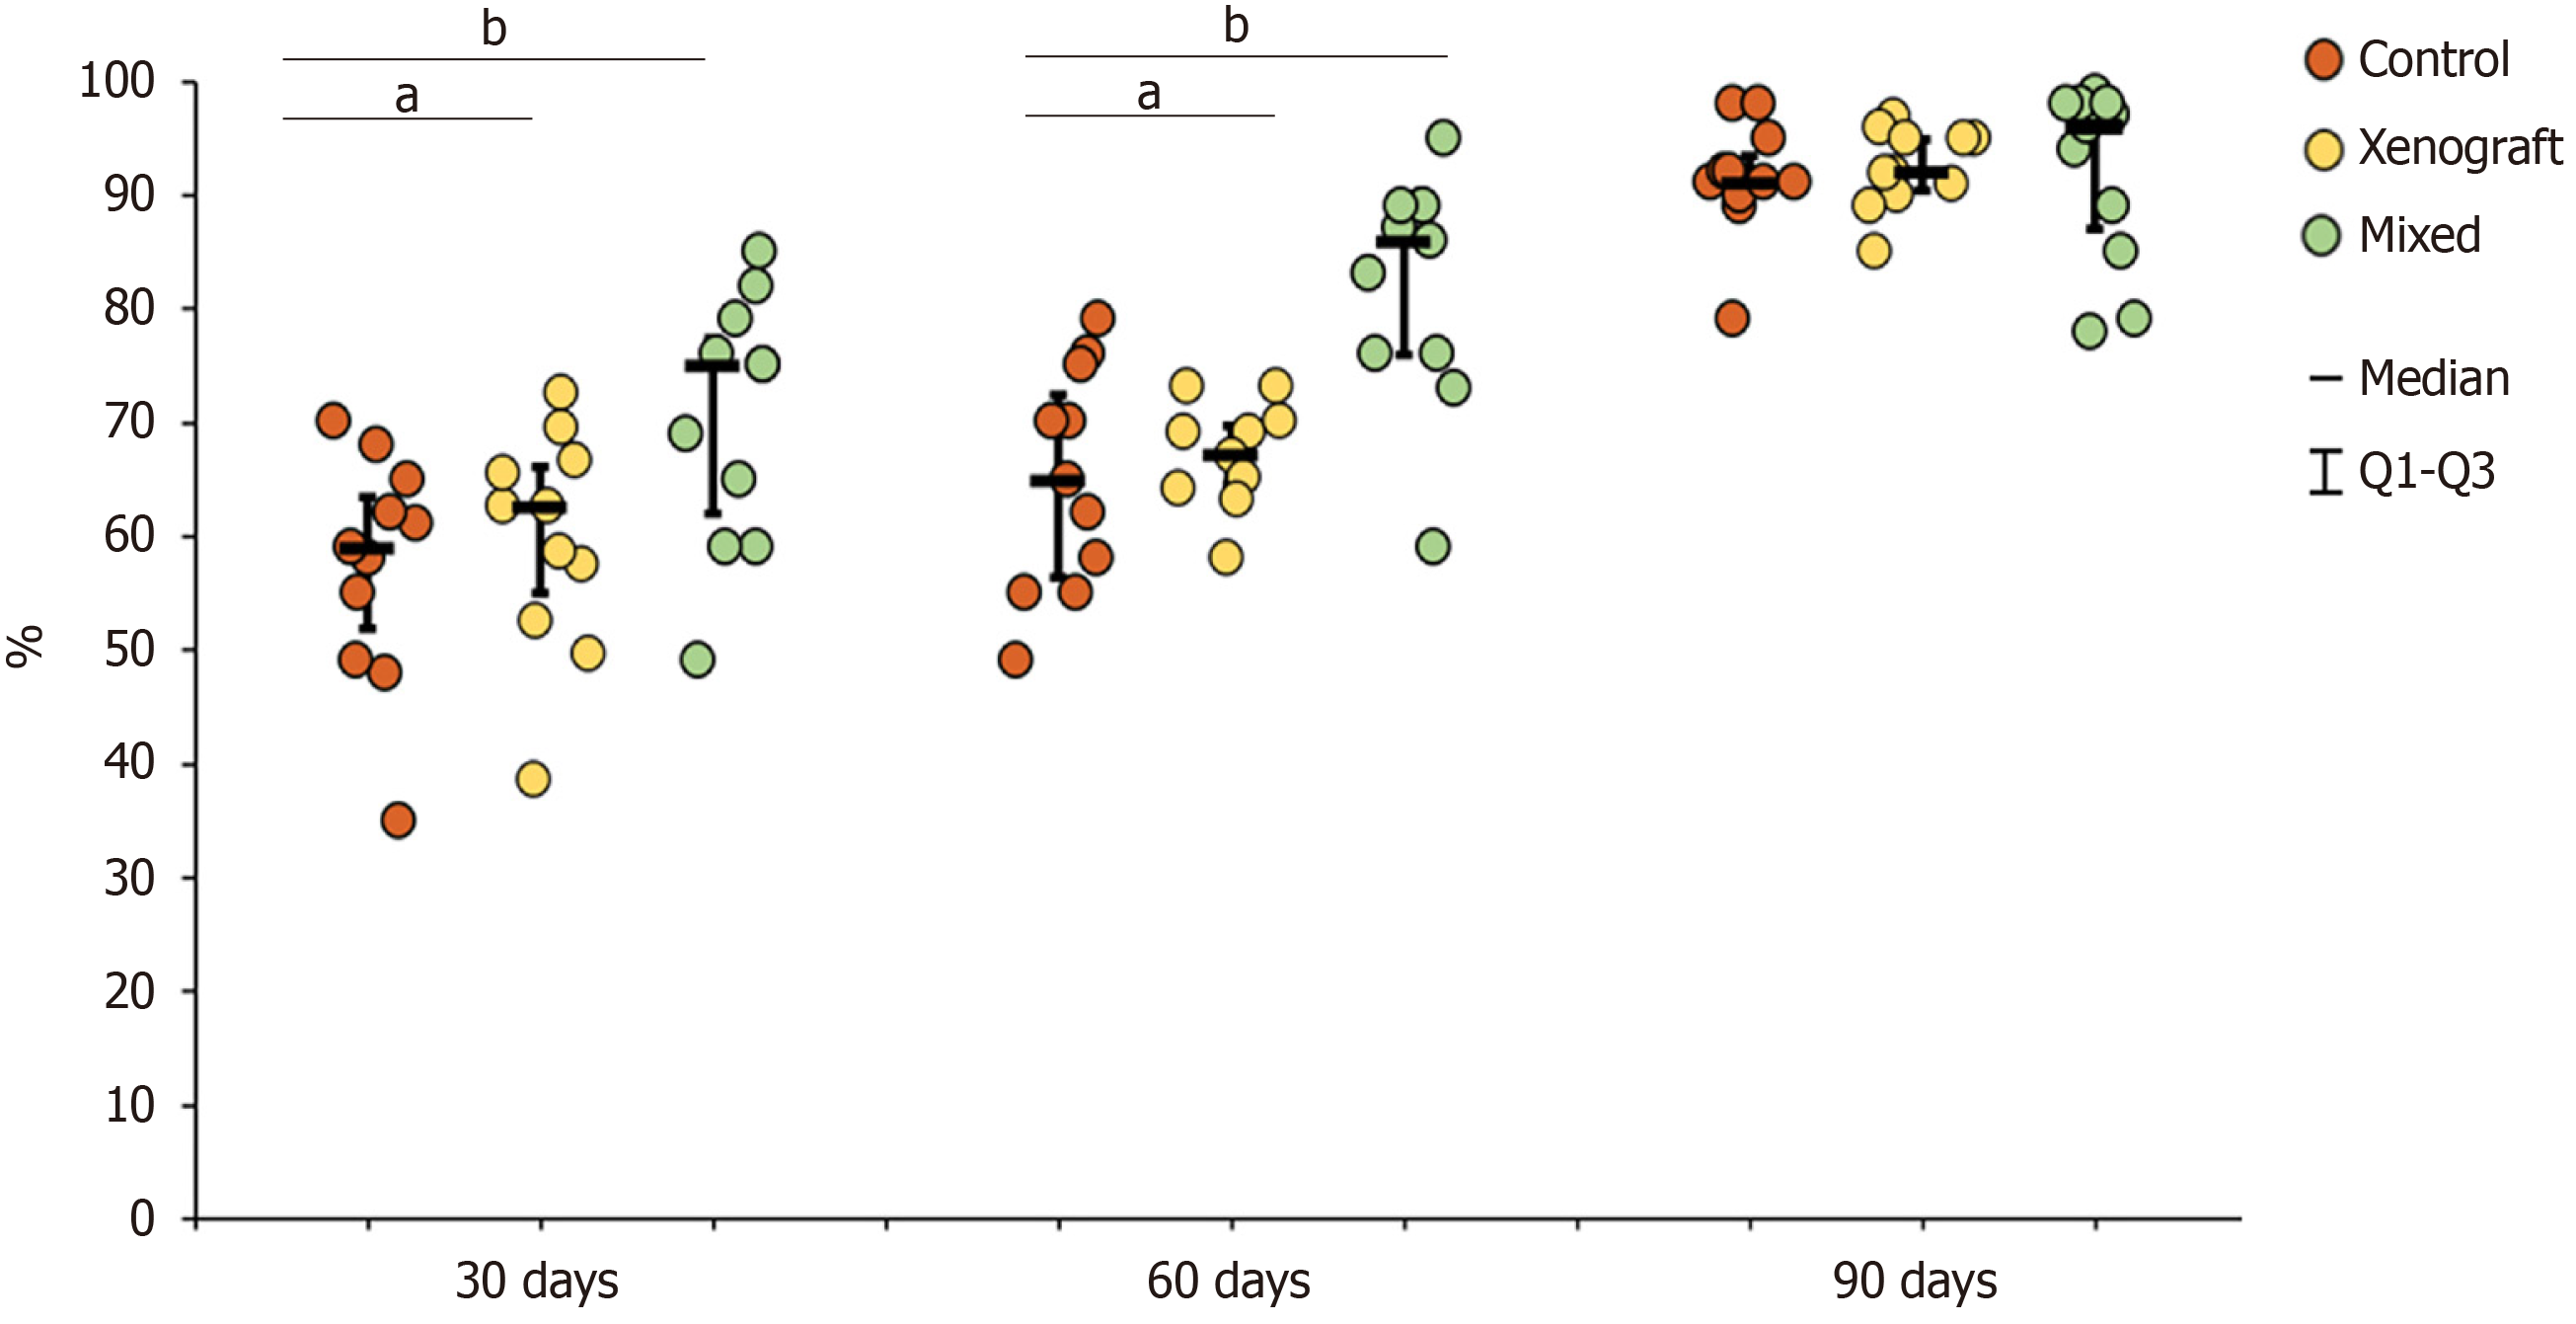
Figure 2 Histological assessment of the percentage of bone tissue within the cortical plate on days 30, 60, and 90.
aP < 0.0167 indicates statistically significant difference in the closure of the cortical plate by newly formed bone tissue between the control and xenograft composite groups; bP < 0.0167 indicates statistically significant difference in the closure of the cortical plate by newly formed bone tissue between the control and mixed composite groups.
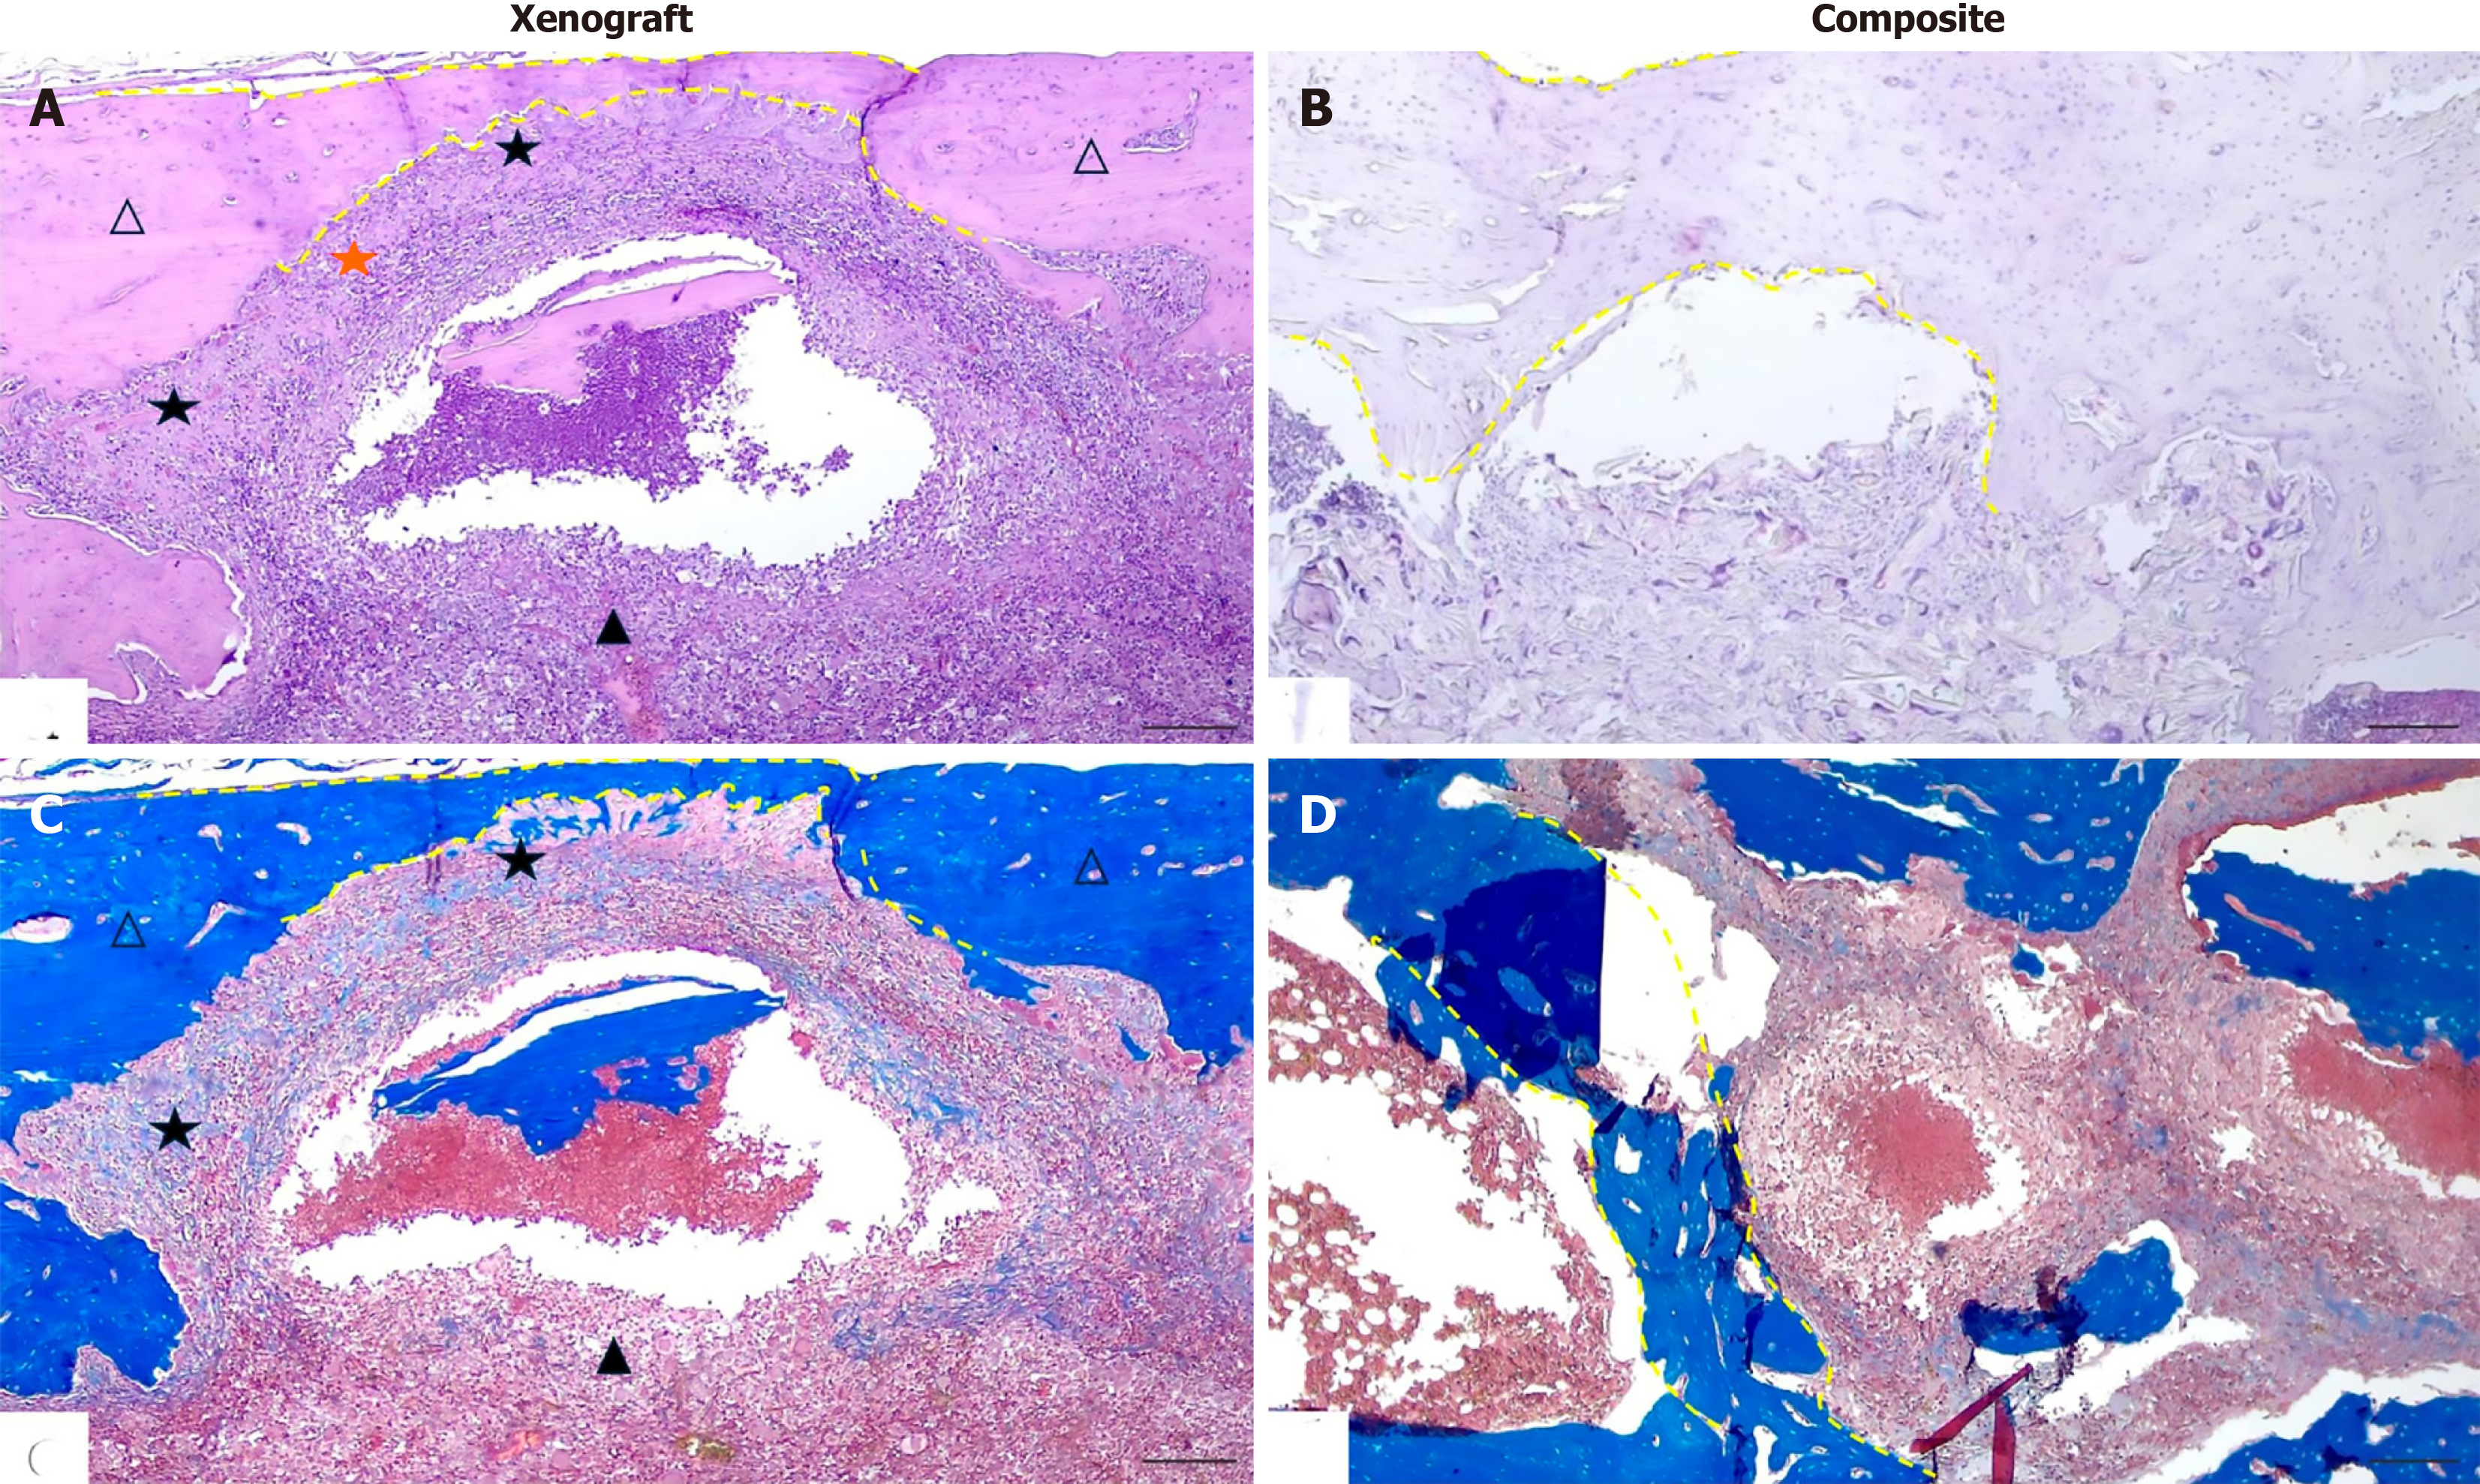
Figure 3 Representative photomicrographs of the cortical plate defect area and the intramedullary space on day 60 after filling the bone defect with xenograft and composite.
A: Xenograft. The defect zone is completely closed by thin newly formed bone tissue (dashed line), consisting of bone trabeculae with prominent lacunae containing osteocytes. Within the intramedullary space, bone xenograft fragments with signs of lysis are identified; B: Composite. The cortical plate defect is fully restored. The composite is undergoing active remodeling and is being replaced by bone tissue; C: Xenograft. The newly formed bone tissue is actively mineralizing. A fragment of remodeling xenograft is present in the intramedullary space; D: Composite. The cortical plate is completely restored. The composite is partially resorbed and is being replaced by mature bone trabeculae. Hematoxylin and eosin staining (A and B). Masson’s trichrome (C and D). Original magnification × 40, scale bar 500 μm. White triangle: Bone plate defect margin. Black triangle: Multinucleated giant cells. Orange five-pointed star: Polymorphonu
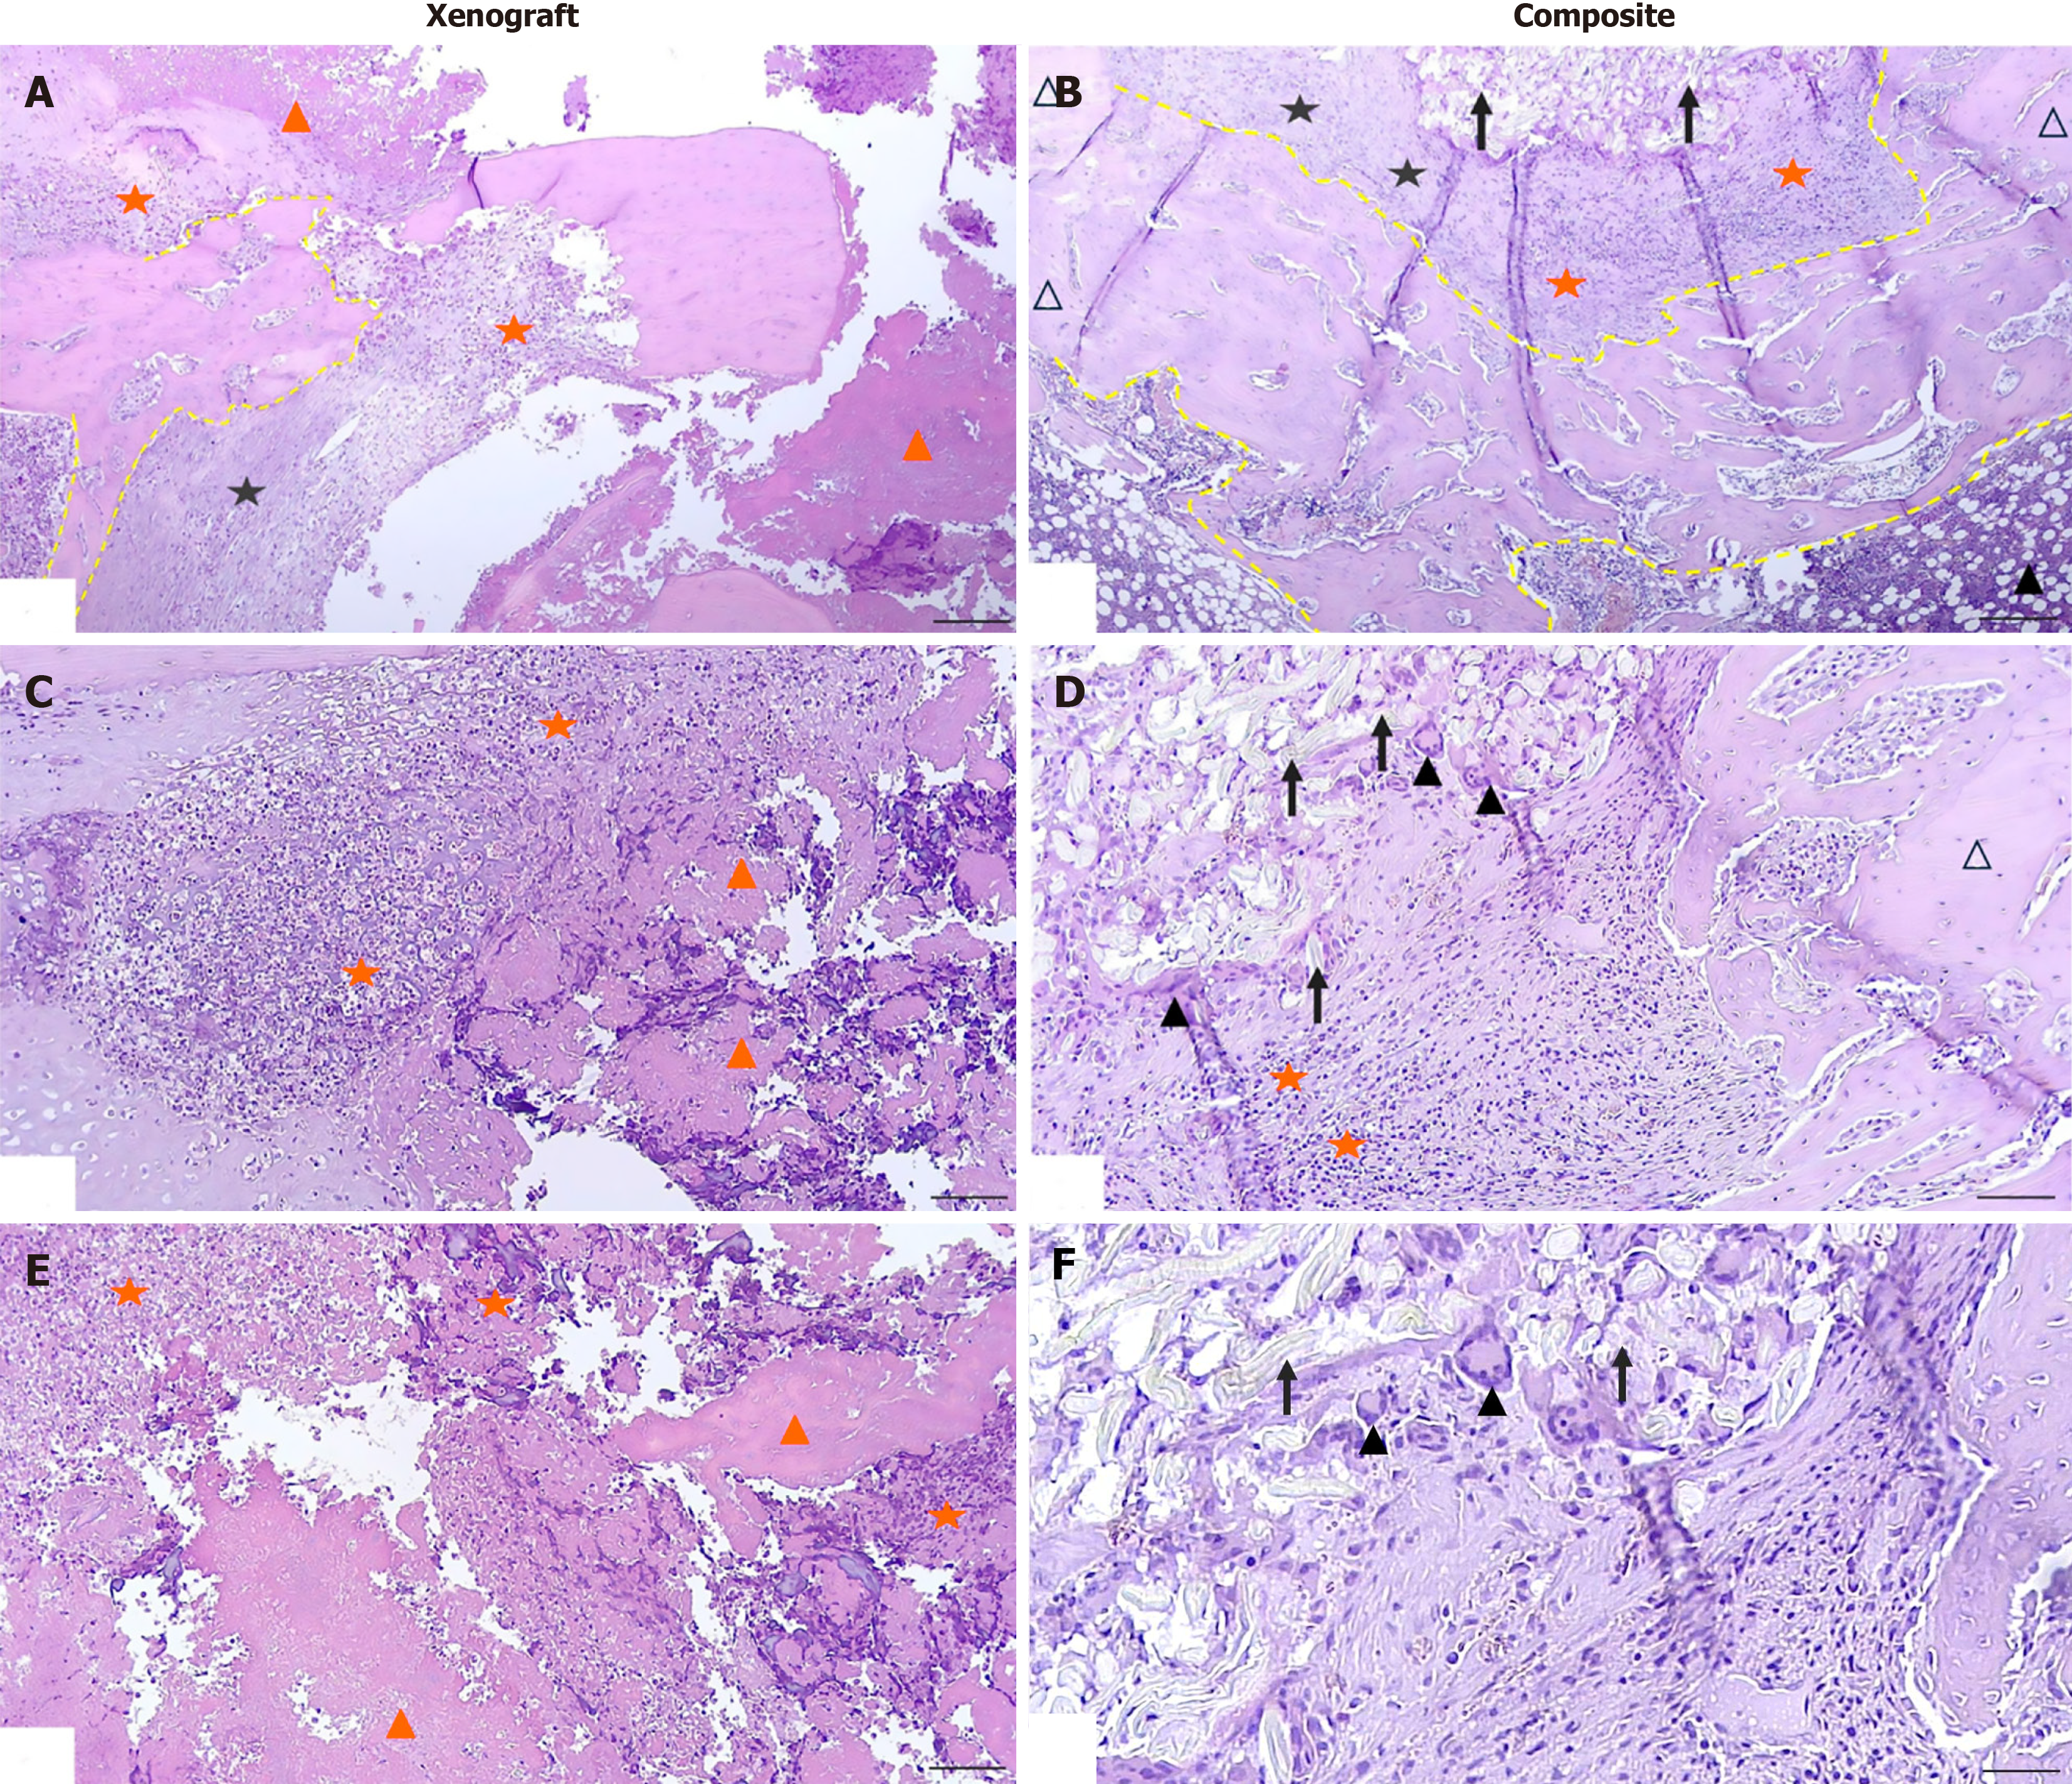
Figure 4 Micrographs of the cortical plate defect zone and the intramedullary space on day 30 after Staphylococcus aureus inoculation.
A: Xenograft group. The cortical defect margin is characterized by areas of bone necrosis and pronounced inflammatory cellular infiltration; B: Сomposite group. Partial extraosseous migration of the composite beyond the defect into the surrounding soft tissues is noted. Newly formed bone tissue (yellow dashed line) is identified in the central zone of the cortical defect, represented by bone trabeculae completely covering the defect. A zone of fibrous tissue with cellular infiltration is detected at the periphery of the defect (∆); C: Xenograft group. Osteocyte lacunae are predominantly empty, and bone trabeculae are fragmented. Diffuse infiltration by polymorphonuclear granulocytes and marked destruction are observed around the necrotic masses. A distinct demarcation zone of inflammatory cells is visible between the necrotic area and the preserved bone tissue; D: Сomposite group. A zone of fibrous tissue with vascularization, pronounced macrophage-histiocytic infiltrate, and single polymorphonuclear granulocytes are observed at the periphery of the composite; E: Xenograft group. Diffuse bone necrosis, massive clusters of polymorphonuclear granulocytes, foci of tissue breakdown, and nuclear detritus; F: Сomposite group. Fragments of pale-stained, homogeneous masses corresponding to nanofibrillated cellulose composite are identified undergoing lysis by macrophages and multinucleated foreign body giant cells. Hematoxylin and eosin staining. Original magnification × 40, scale bar 500 μm (A and B); original magnification × 100, scale bar 200 μm (C and D); original magnification × 200, scale bar 100 μm (E and F), White triangle: Bone plate defect margin. Black triangle: Multinucleated giant cells. Orange five-pointed star: Polymorphonuclear granulocytes. Black five-pointed star: Lymphocytes and plasma cells. Black arrow: Nanofibrillated cellulose. Orange triangle: Necrotic tissue.
- Citation: Tuleubayev BE, Makhatov BK, Vinokurov VA, Kamyshanskiy YK, Kossilova YY, Akhmetova SB, Koshanova AA, Davletbaev MZ, Arutyunyan MG. Osteoreparative potential of nanofibrillated cellulose, xenograft, and butvar-phenolic adhesive-based composite. World J Orthop 2026; 17(11): 118182
- URL: https://www.wjgnet.com/2218-5836/full/v17/i11/118182.htm
- DOI: https://dx.doi.org/10.5312/wjo.118182