
















Copyright: ©Author(s) 2026.
World J Gastrointest Surg. Oct 27, 2026; 18(10): 123695
Published online Oct 27, 2026. doi: 10.4240/wjgs.123695
Published online Oct 27, 2026. doi: 10.4240/wjgs.123695
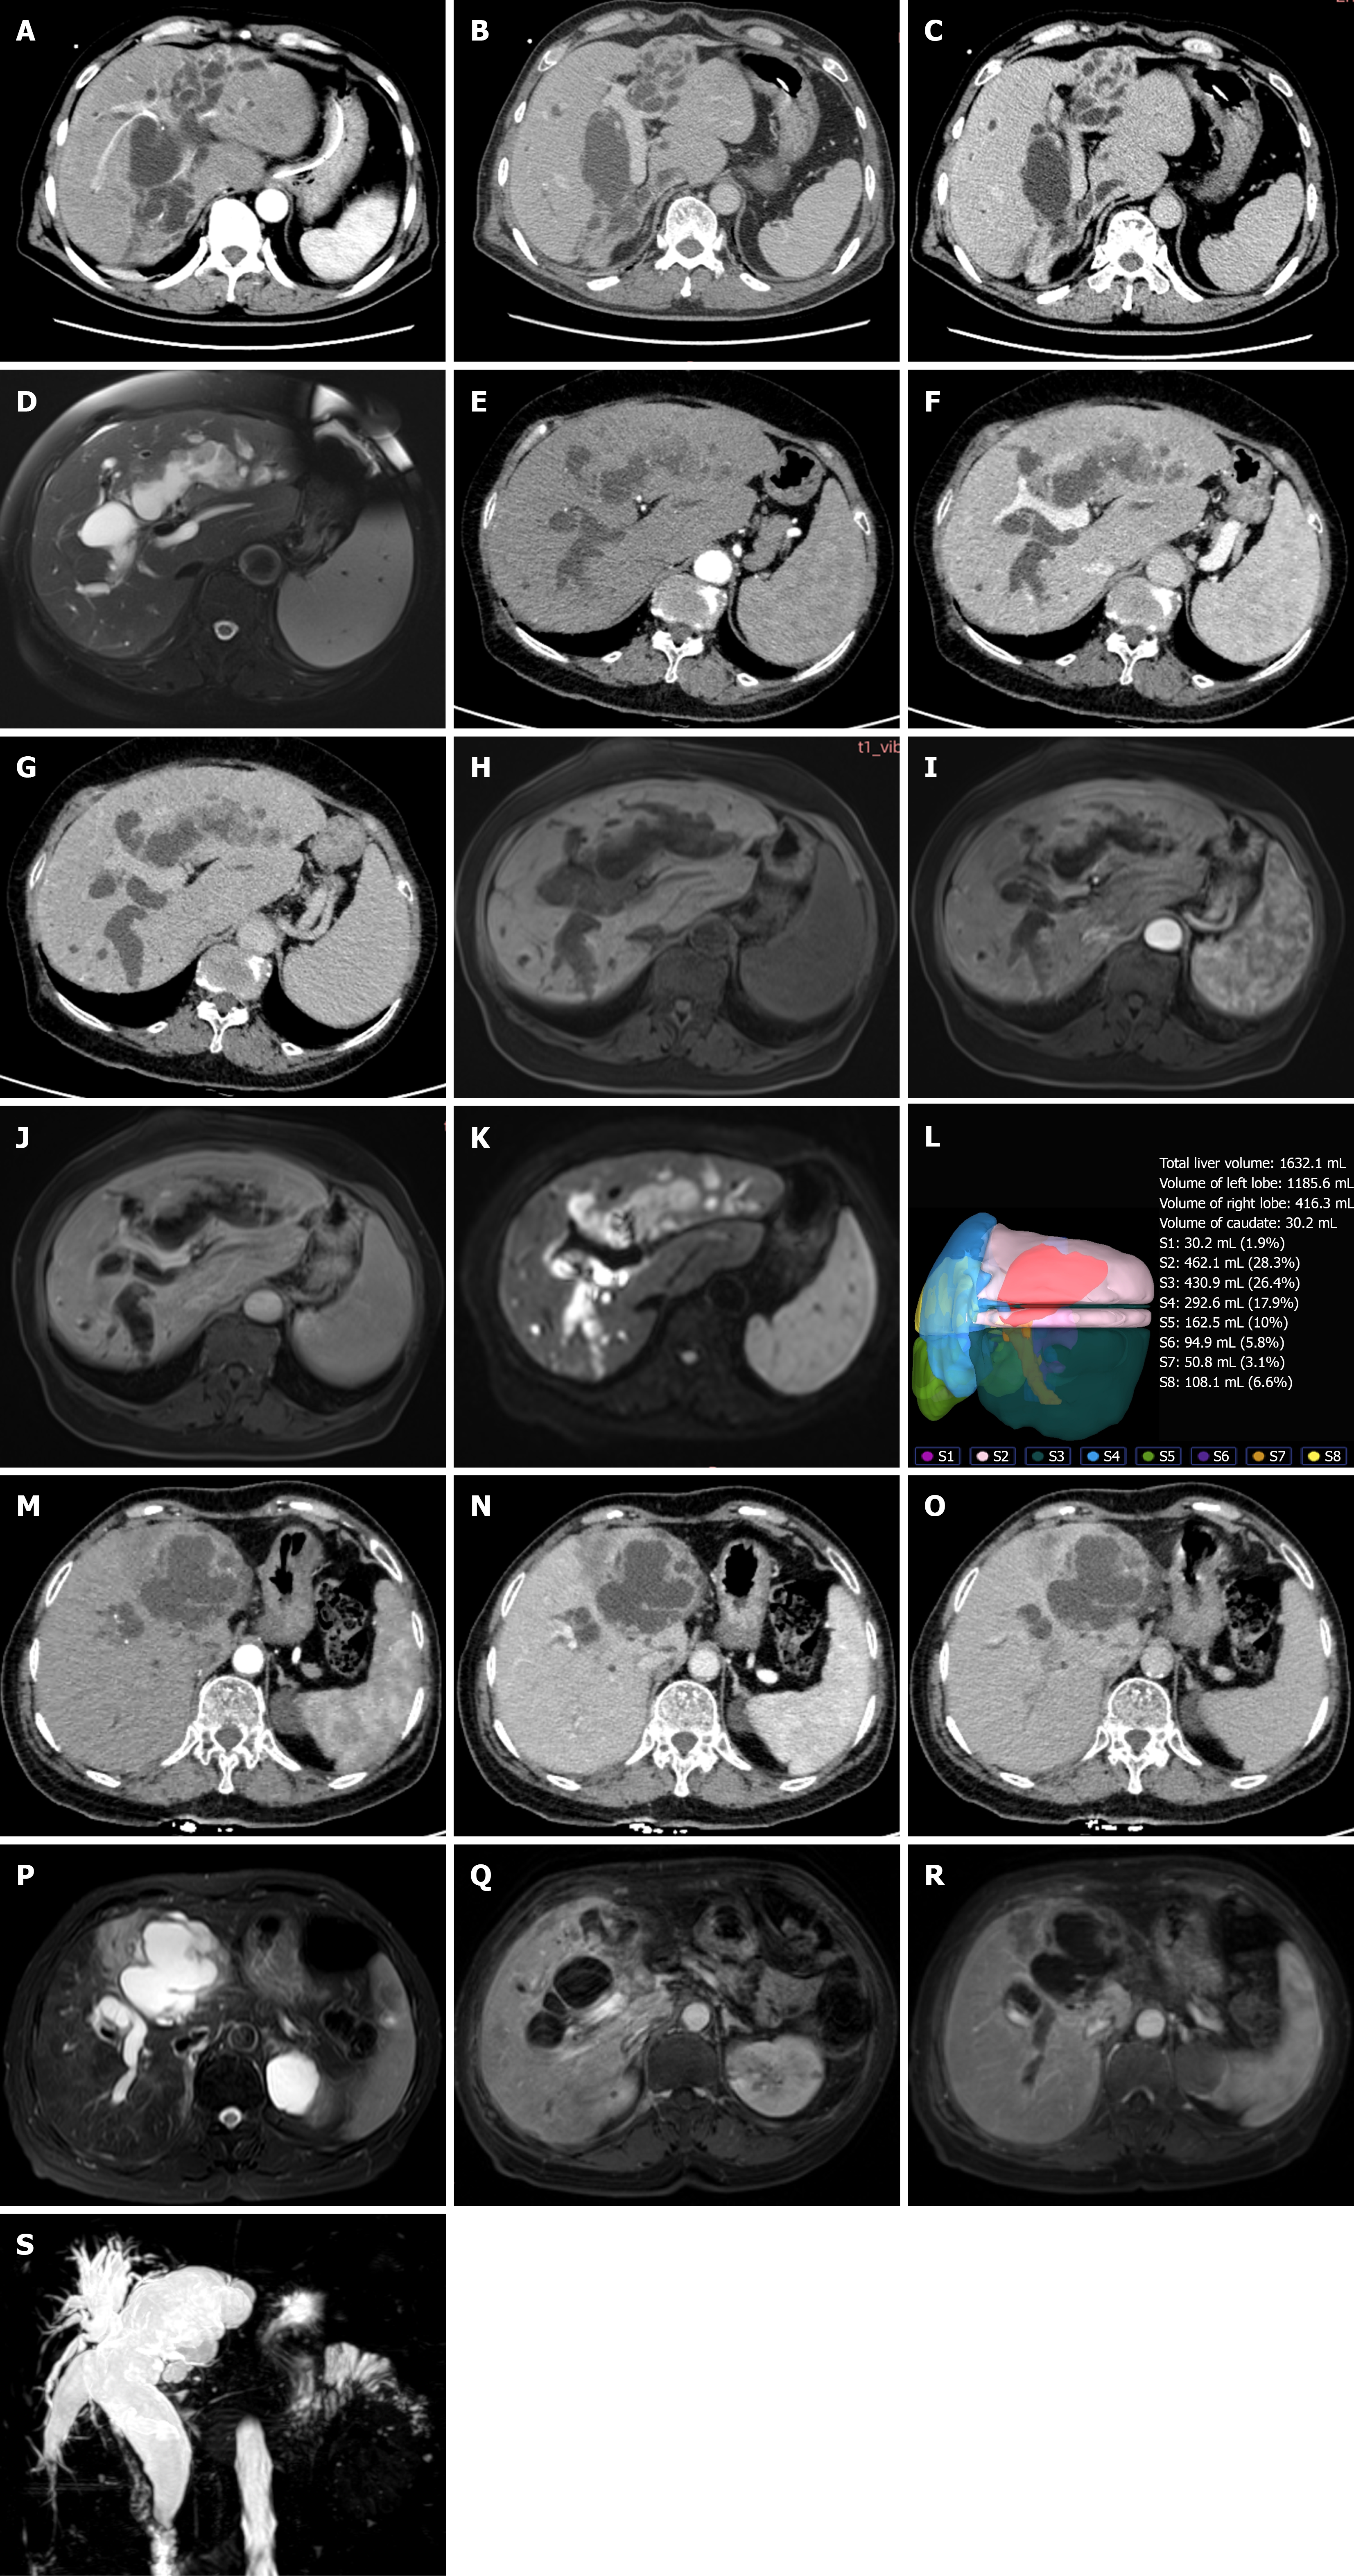
Figure 1 Preoperative abdominal contrast-enhanced computed tomography, abdominal contrast-enhanced magnetic resonance imaging, and magnetic resonance cholangiopancreatography of patients.
A: Preoperative abdominal contrast-enhanced computed tomography (CT) images of patient 1 showing schistosomiasis-related cirrhosis, diffuse intrahepatic bile duct dilatation, and atrophy of the left lateral and right posterior lobes. Multiple intraductal papillary lesions show mild arterial phase enhancement; B: The lesions show relative hypoattenuation in the portal venous phase; C: The lesions show persistent hypoattenuation in the delayed phase; D: The papillary lesions of patient 2 appear mildly hyperintense on T2-weighted imaging; E: Preoperative abdominal contrast-enhanced CT images of patient 2 showing schistosomiasis-related cirrhosis with intrahepatic bile duct dilatation and multiple intraductal papillary lesions. The lesions show mild enhancement in the arterial phase; F: The lesions show relative hypoattenuation in the portal venous; G: The lesions showdelayed phases; H: The papillary lesions of patient 2 appear hypointense on T1-weighted imaging of Preoperative abdominal contrast-enhanced magnetic resonance imaging (MRI); I: The papillary lesions show mild enhancement in the arterial phase; J: The lesions have low signal intensity in the venous phase; K: Diffusion-weighted imaging of patient 2 revealed mild hyperintensity; L: Preoperative three-dimensional reconstruction of patient 2 shows a total liver volume of 1632.1 ml; M: Preoperative contrast-enhanced CT images of patient 3 reveal bile duct dilatation with atrophy of the left and caudate lobes and intraductal papillary masses in the left lobe; the lesions show mild enhancement in the arterial phase; N: The lesions show relative hypoattenuation in the portal venous phase; O: The lesions show relative hypoattenuation in the delayed phases; P: T2-weighted image shows multiple intraductal papillary masses; Q: Contrast-enhanced MRI shows mild arterial enhancement; R: Contrast-enhanced MRI shows low signal intensity in the portal venous phase; S: Magnetic resonance cholangiopancreatography confirms diffuse dilatation of the intrahepatic and extrahepatic bile ducts.
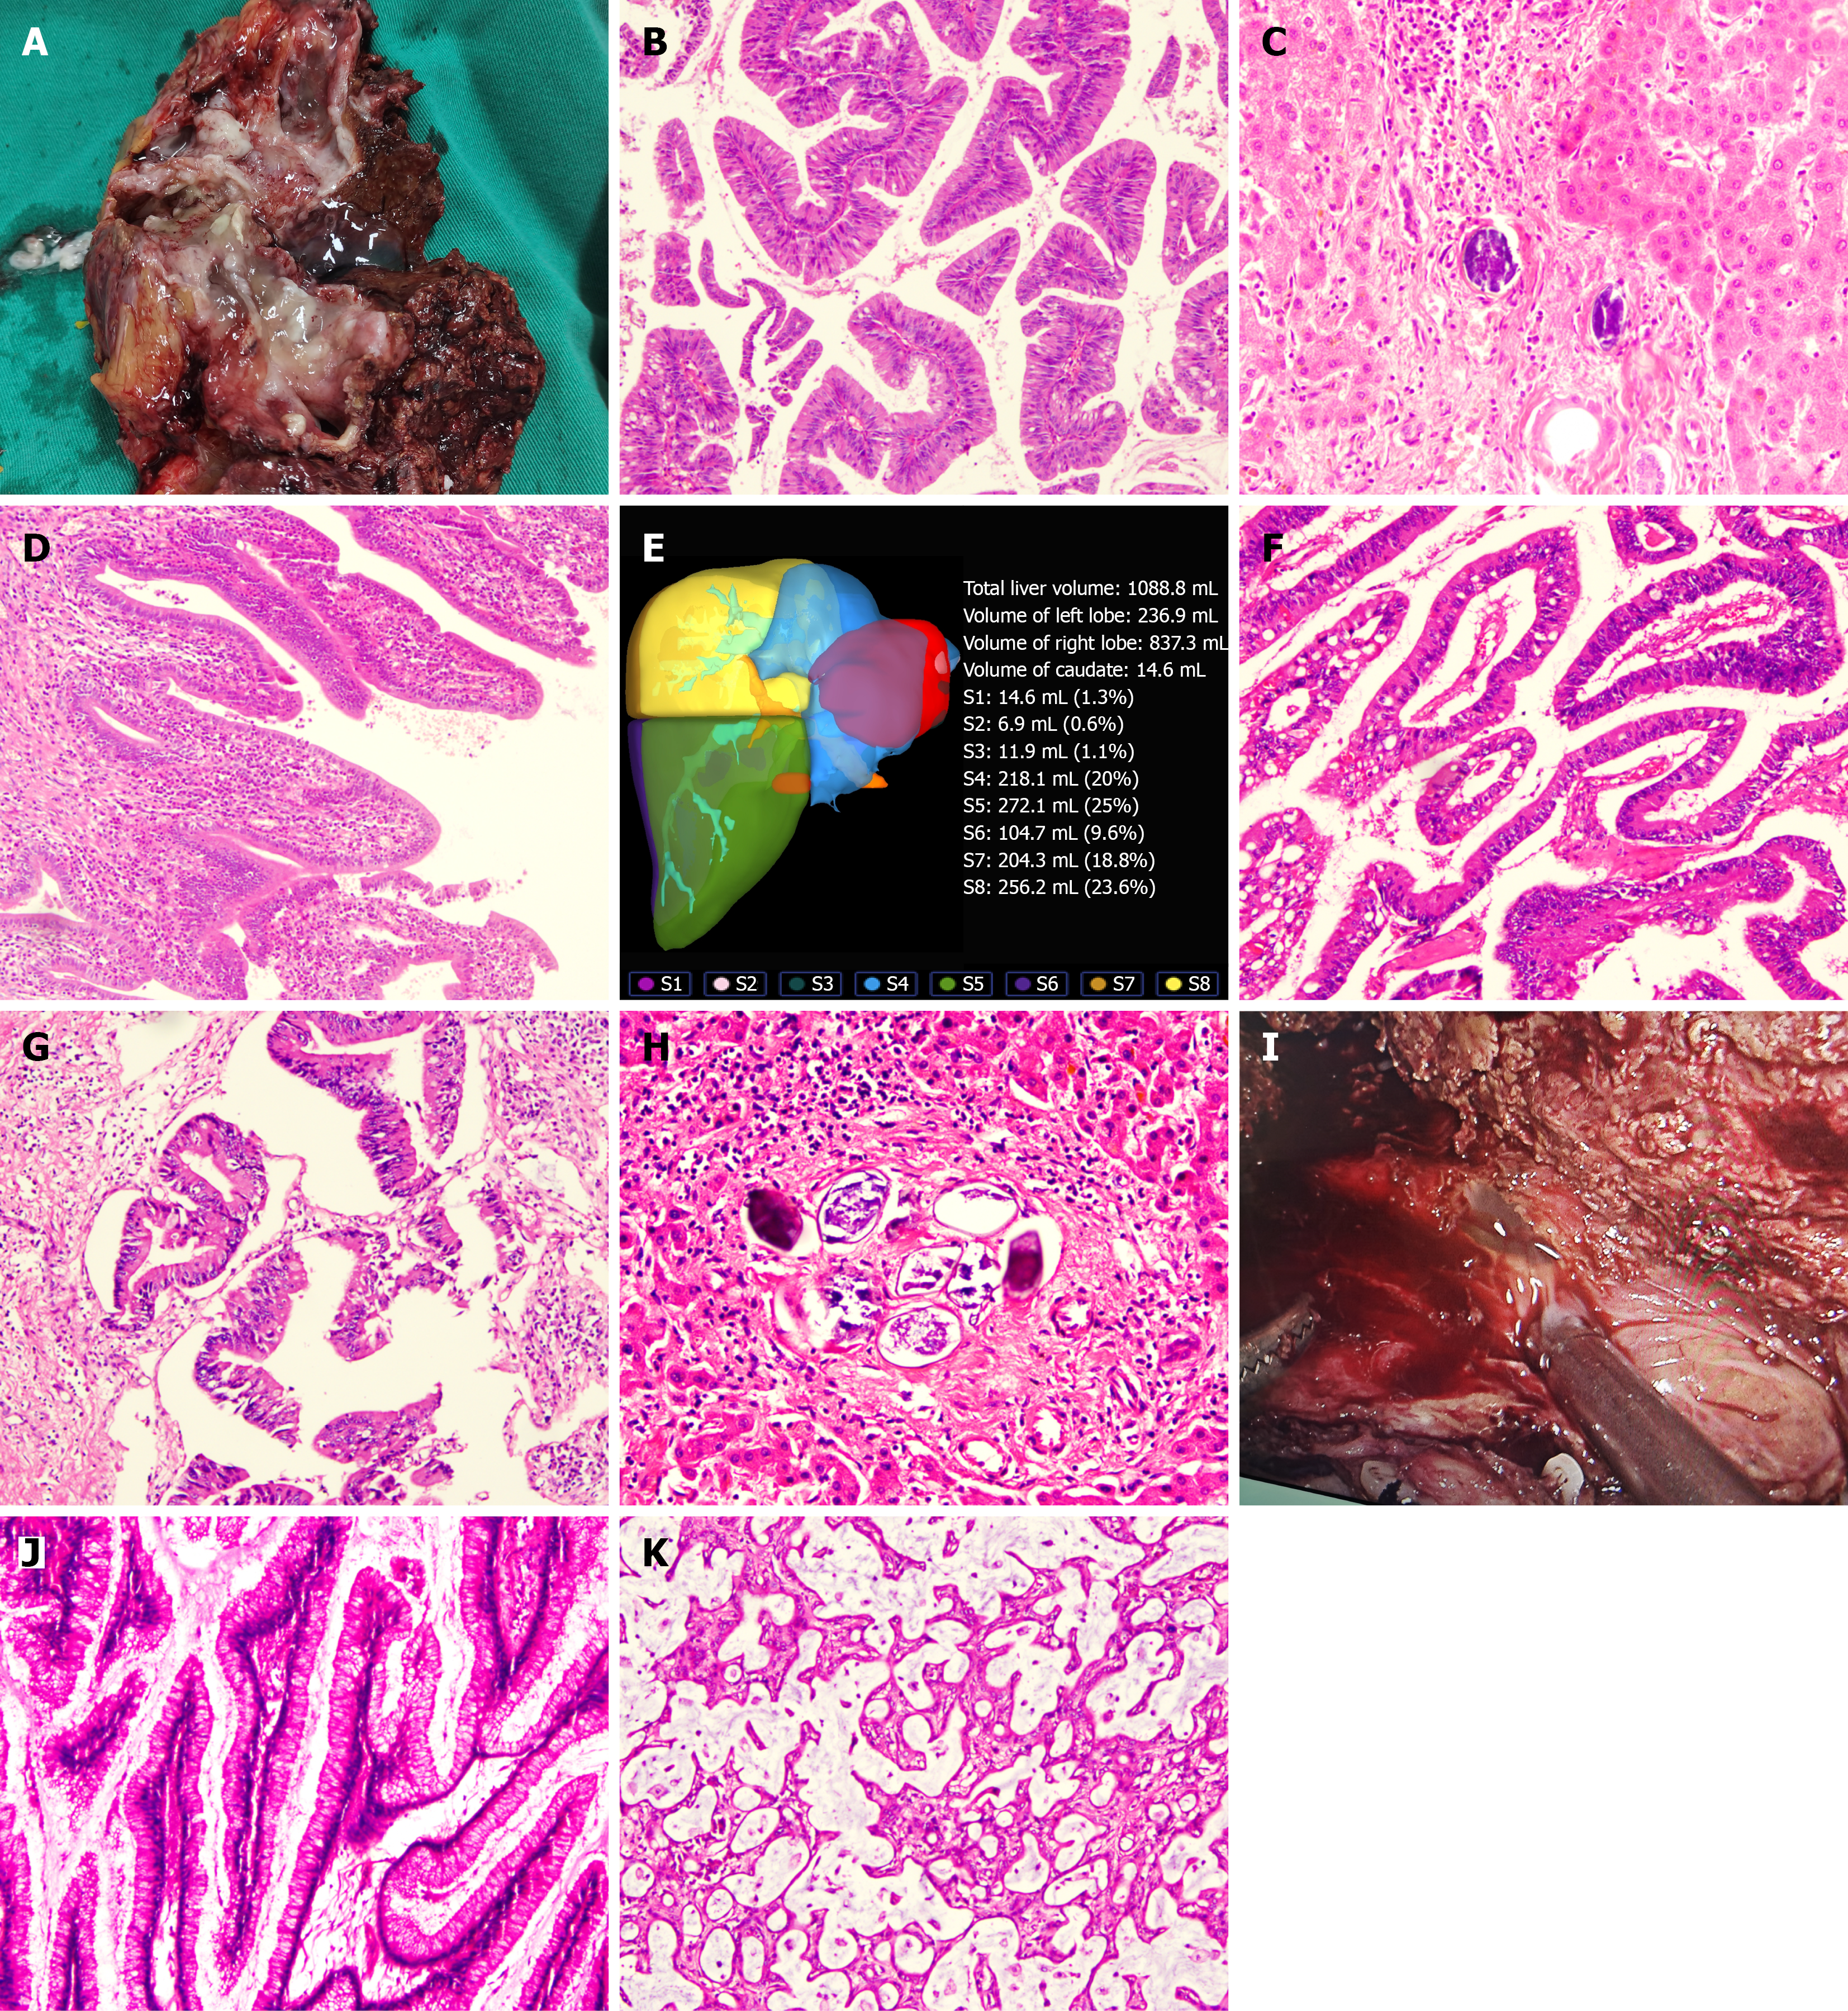
Figure 2 Gross specimen, pathology of patients.
A: Gross specimen of patient 1 showing markedly dilated bile ducts filled with mucin and a papillary mass; pathology of patient 1 (B-D); B: Papillary architecture with fibrovascular cores on histopathological examination [hematoxylin and eosin (HE) × 100]; C: Schi
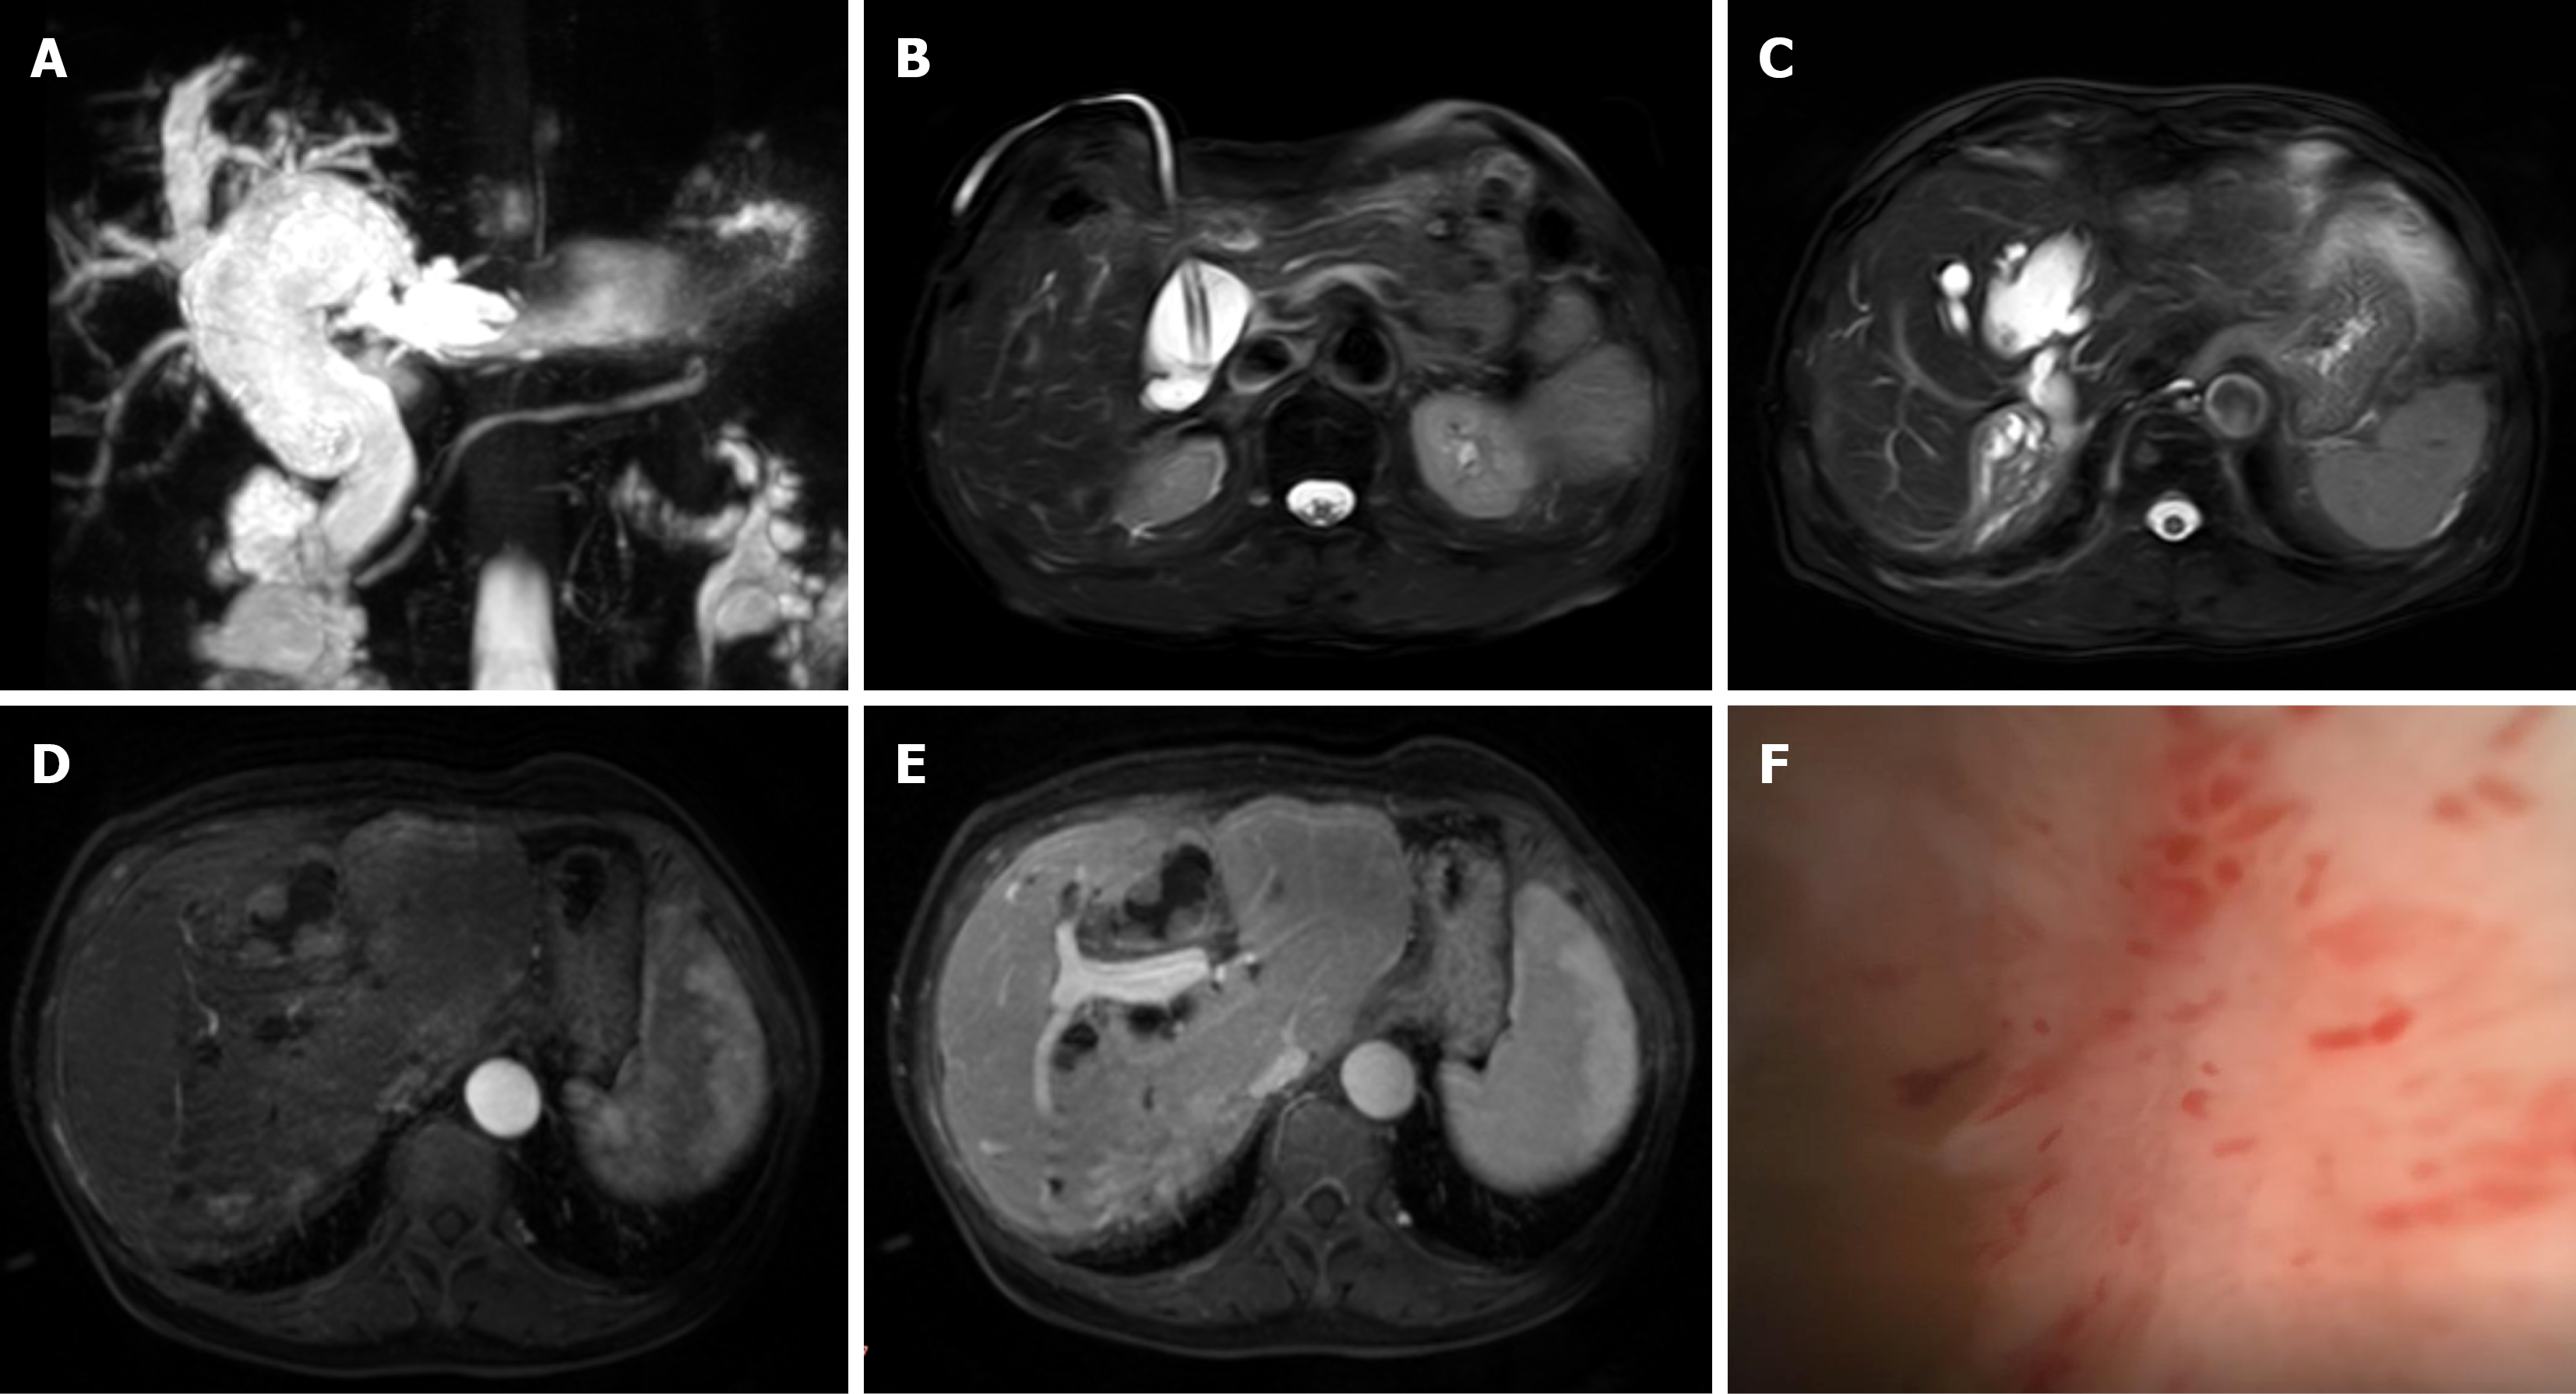
Figure 3 Postoperative magnetic resonance imaging and cholangioscopy of patient 1 and patient 2.
Postoperative magnetic resonance imaging (MRI) of patient 1 (A-C); A: Postoperative magnetic resonance cholangiopancreatography showing dilatation of the intrahepatic and extrahepatic bile ducts; B: T2-weighted image showing a T-tube within the common bile duct; C: T2-weighted imaging showing numerous papillary lesions within the dilated bile ducts of the atrophic right posterior lobe; D and E: Postoperative contrast-enhanced MRI of patient 2 showing residual papillary lesions exhibiting mild arterial enhancement (D) and appearing isointense in the venous phase (E) within dilated bile ducts; F: Percutaneous transhepatic cholangioscopy via T-tube of patient 2 showing bleeding intraductal papillary lesions.
- Citation: Yang YL, Zhang TQ, Le WJ, Zhou L, Cheng H, Li YJ, Zhang KM, Yang ZC, Peng T, Lu HF. Debulking surgery for non-radically resectable intraductal papillary neoplasm of the bile duct: Three case reports and literature review. World J Gastrointest Surg 2026; 18(10): 123695
- URL: https://www.wjgnet.com/1948-9366/full/v18/i10/123695.htm
- DOI: https://dx.doi.org/10.4240/wjgs.123695