
















Copyright: ©Author(s) 2026.
World J Gastrointest Surg. Oct 27, 2026; 18(10): 122861
Published online Oct 27, 2026. doi: 10.4240/wjgs.122861
Published online Oct 27, 2026. doi: 10.4240/wjgs.122861
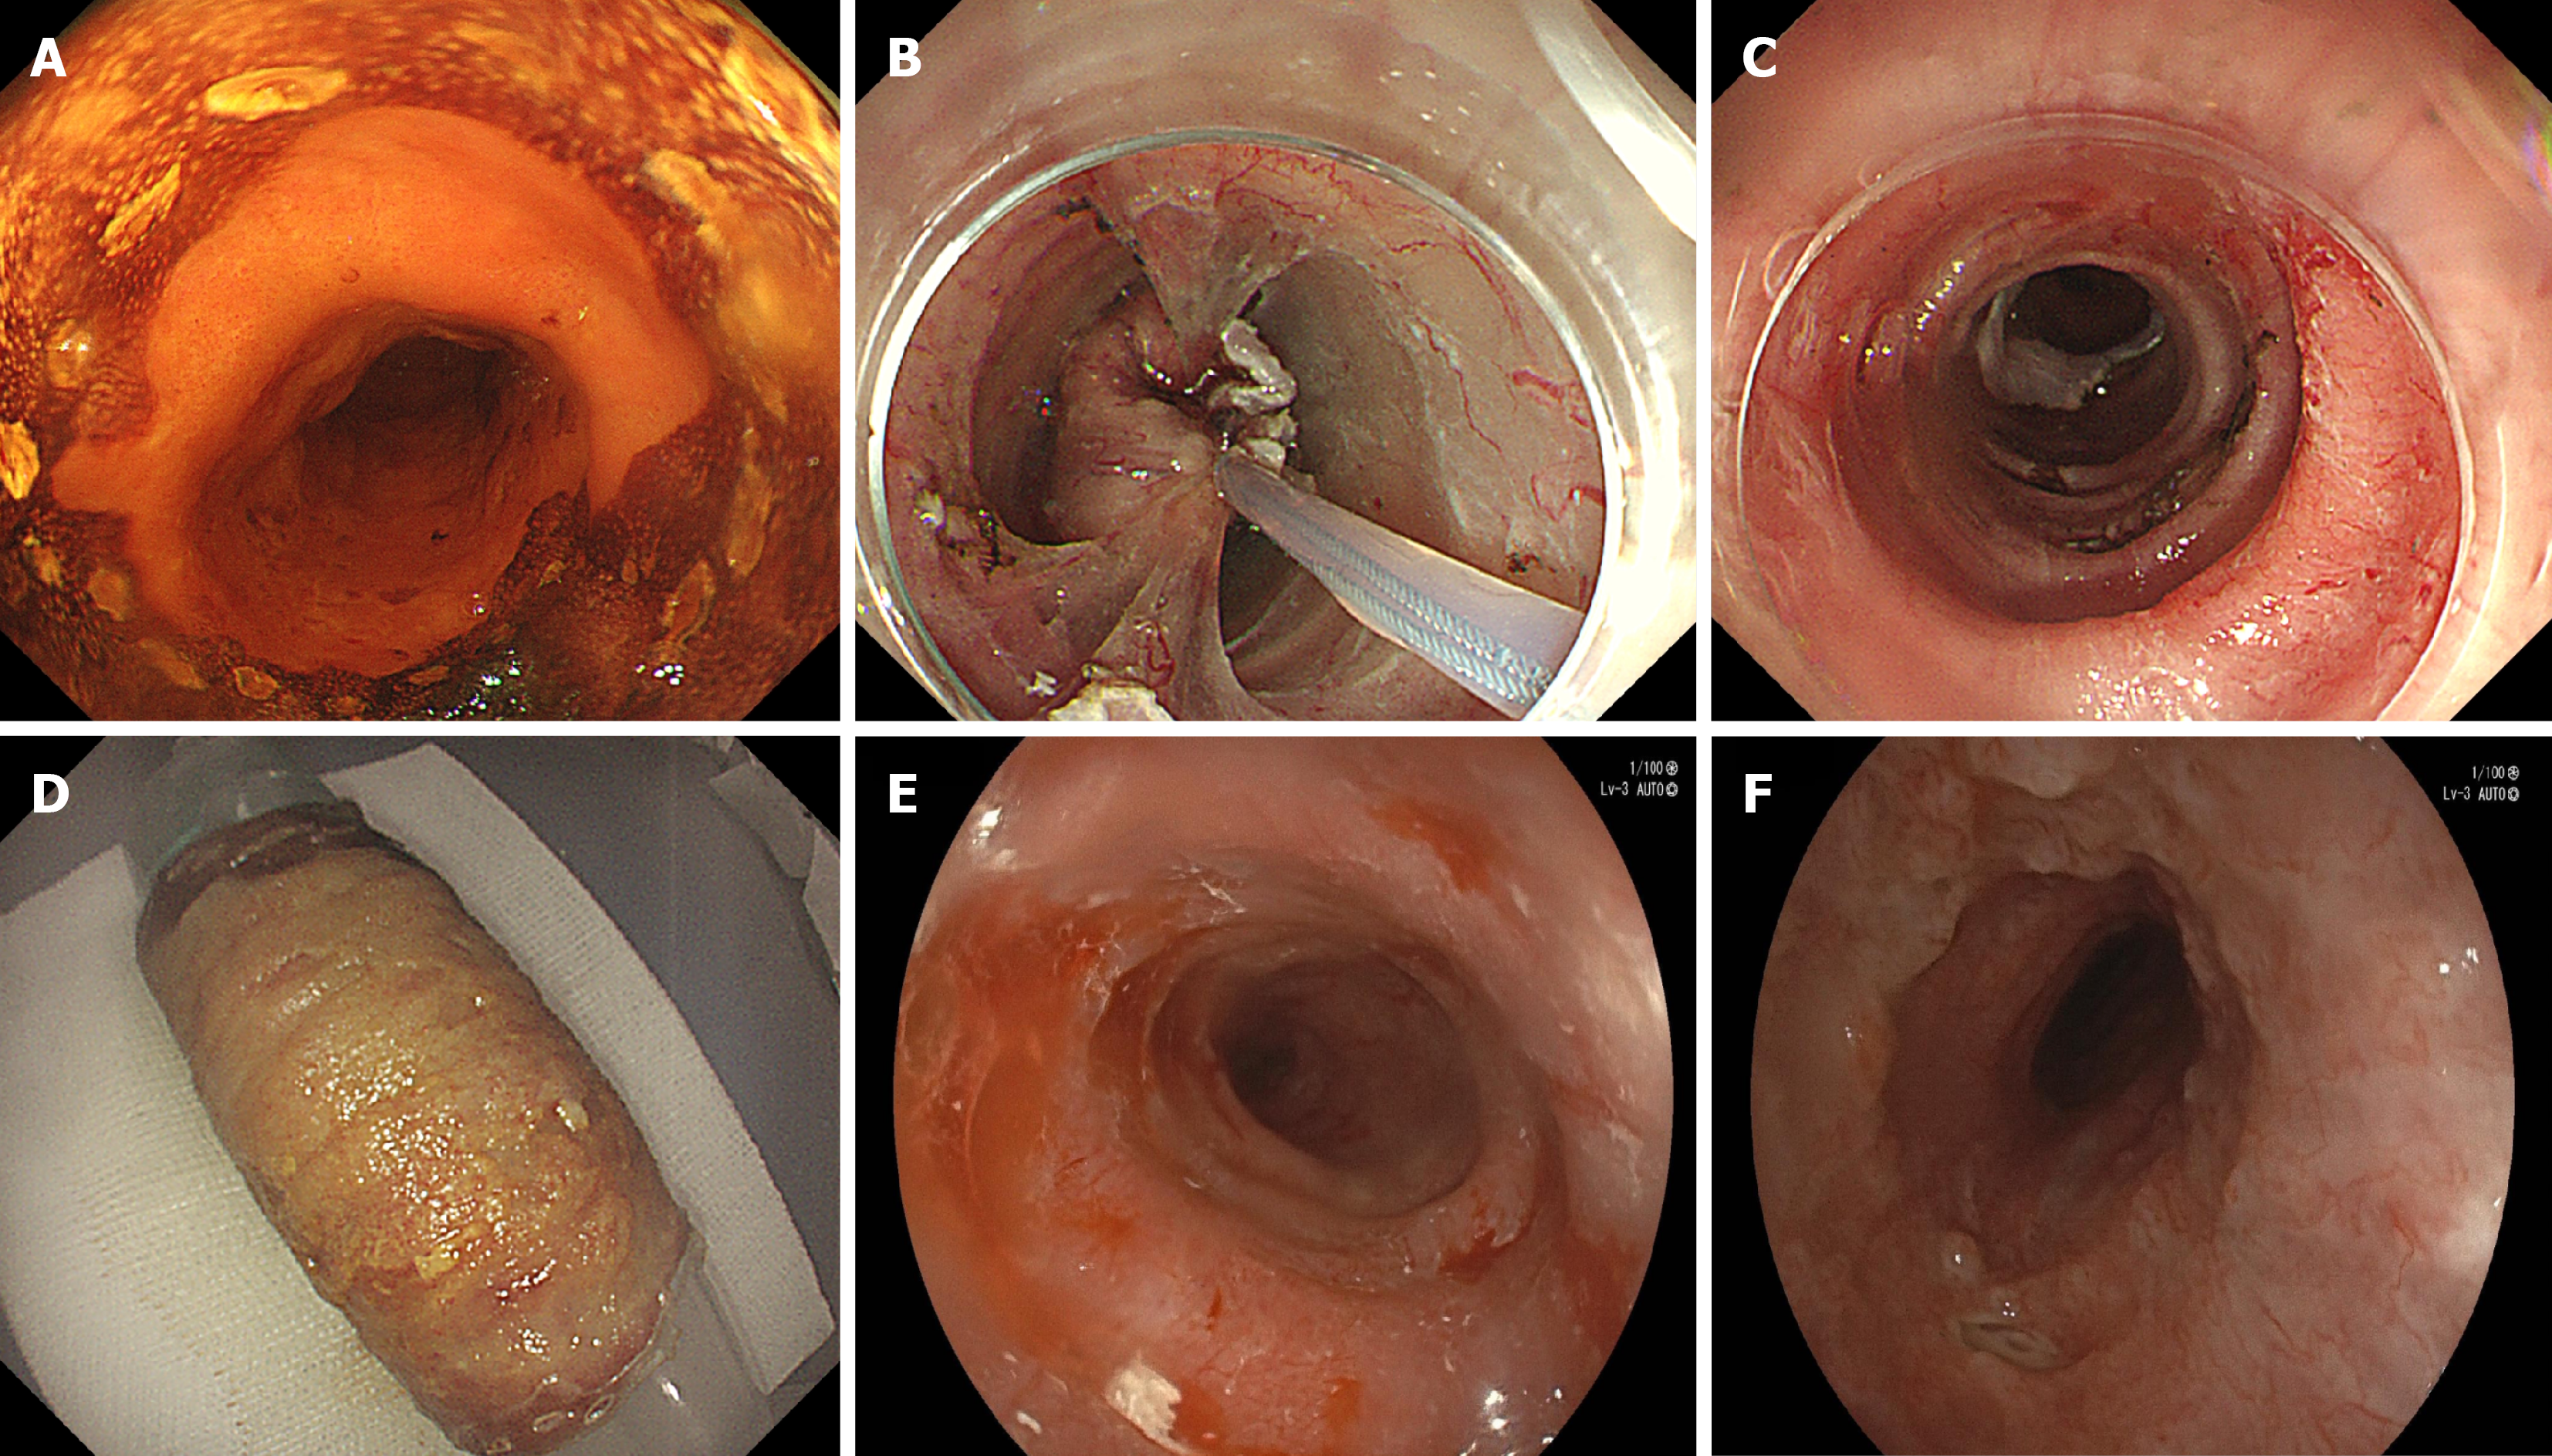
Figure 1 Surgical procedure and postoperative multipoint steroid injections for stricture prevention.
A: Lesion located 33-39 cm from incisors, involving the entire circumference; B: Double-tunnel technique and snare traction providing adequate exposure of the wound, reducing complications; C: Postoperative wound intact without muscular layer injury; D: Resected specimen en bloc; E: Multipoint submucosal triamcinolone injection one week post-endoscopic submucosal dissection (December 12, 2022); F: Multipoint submucosal triamcinolone injection two weeks post-endoscopic submucosal dissection (December 19, 2022).
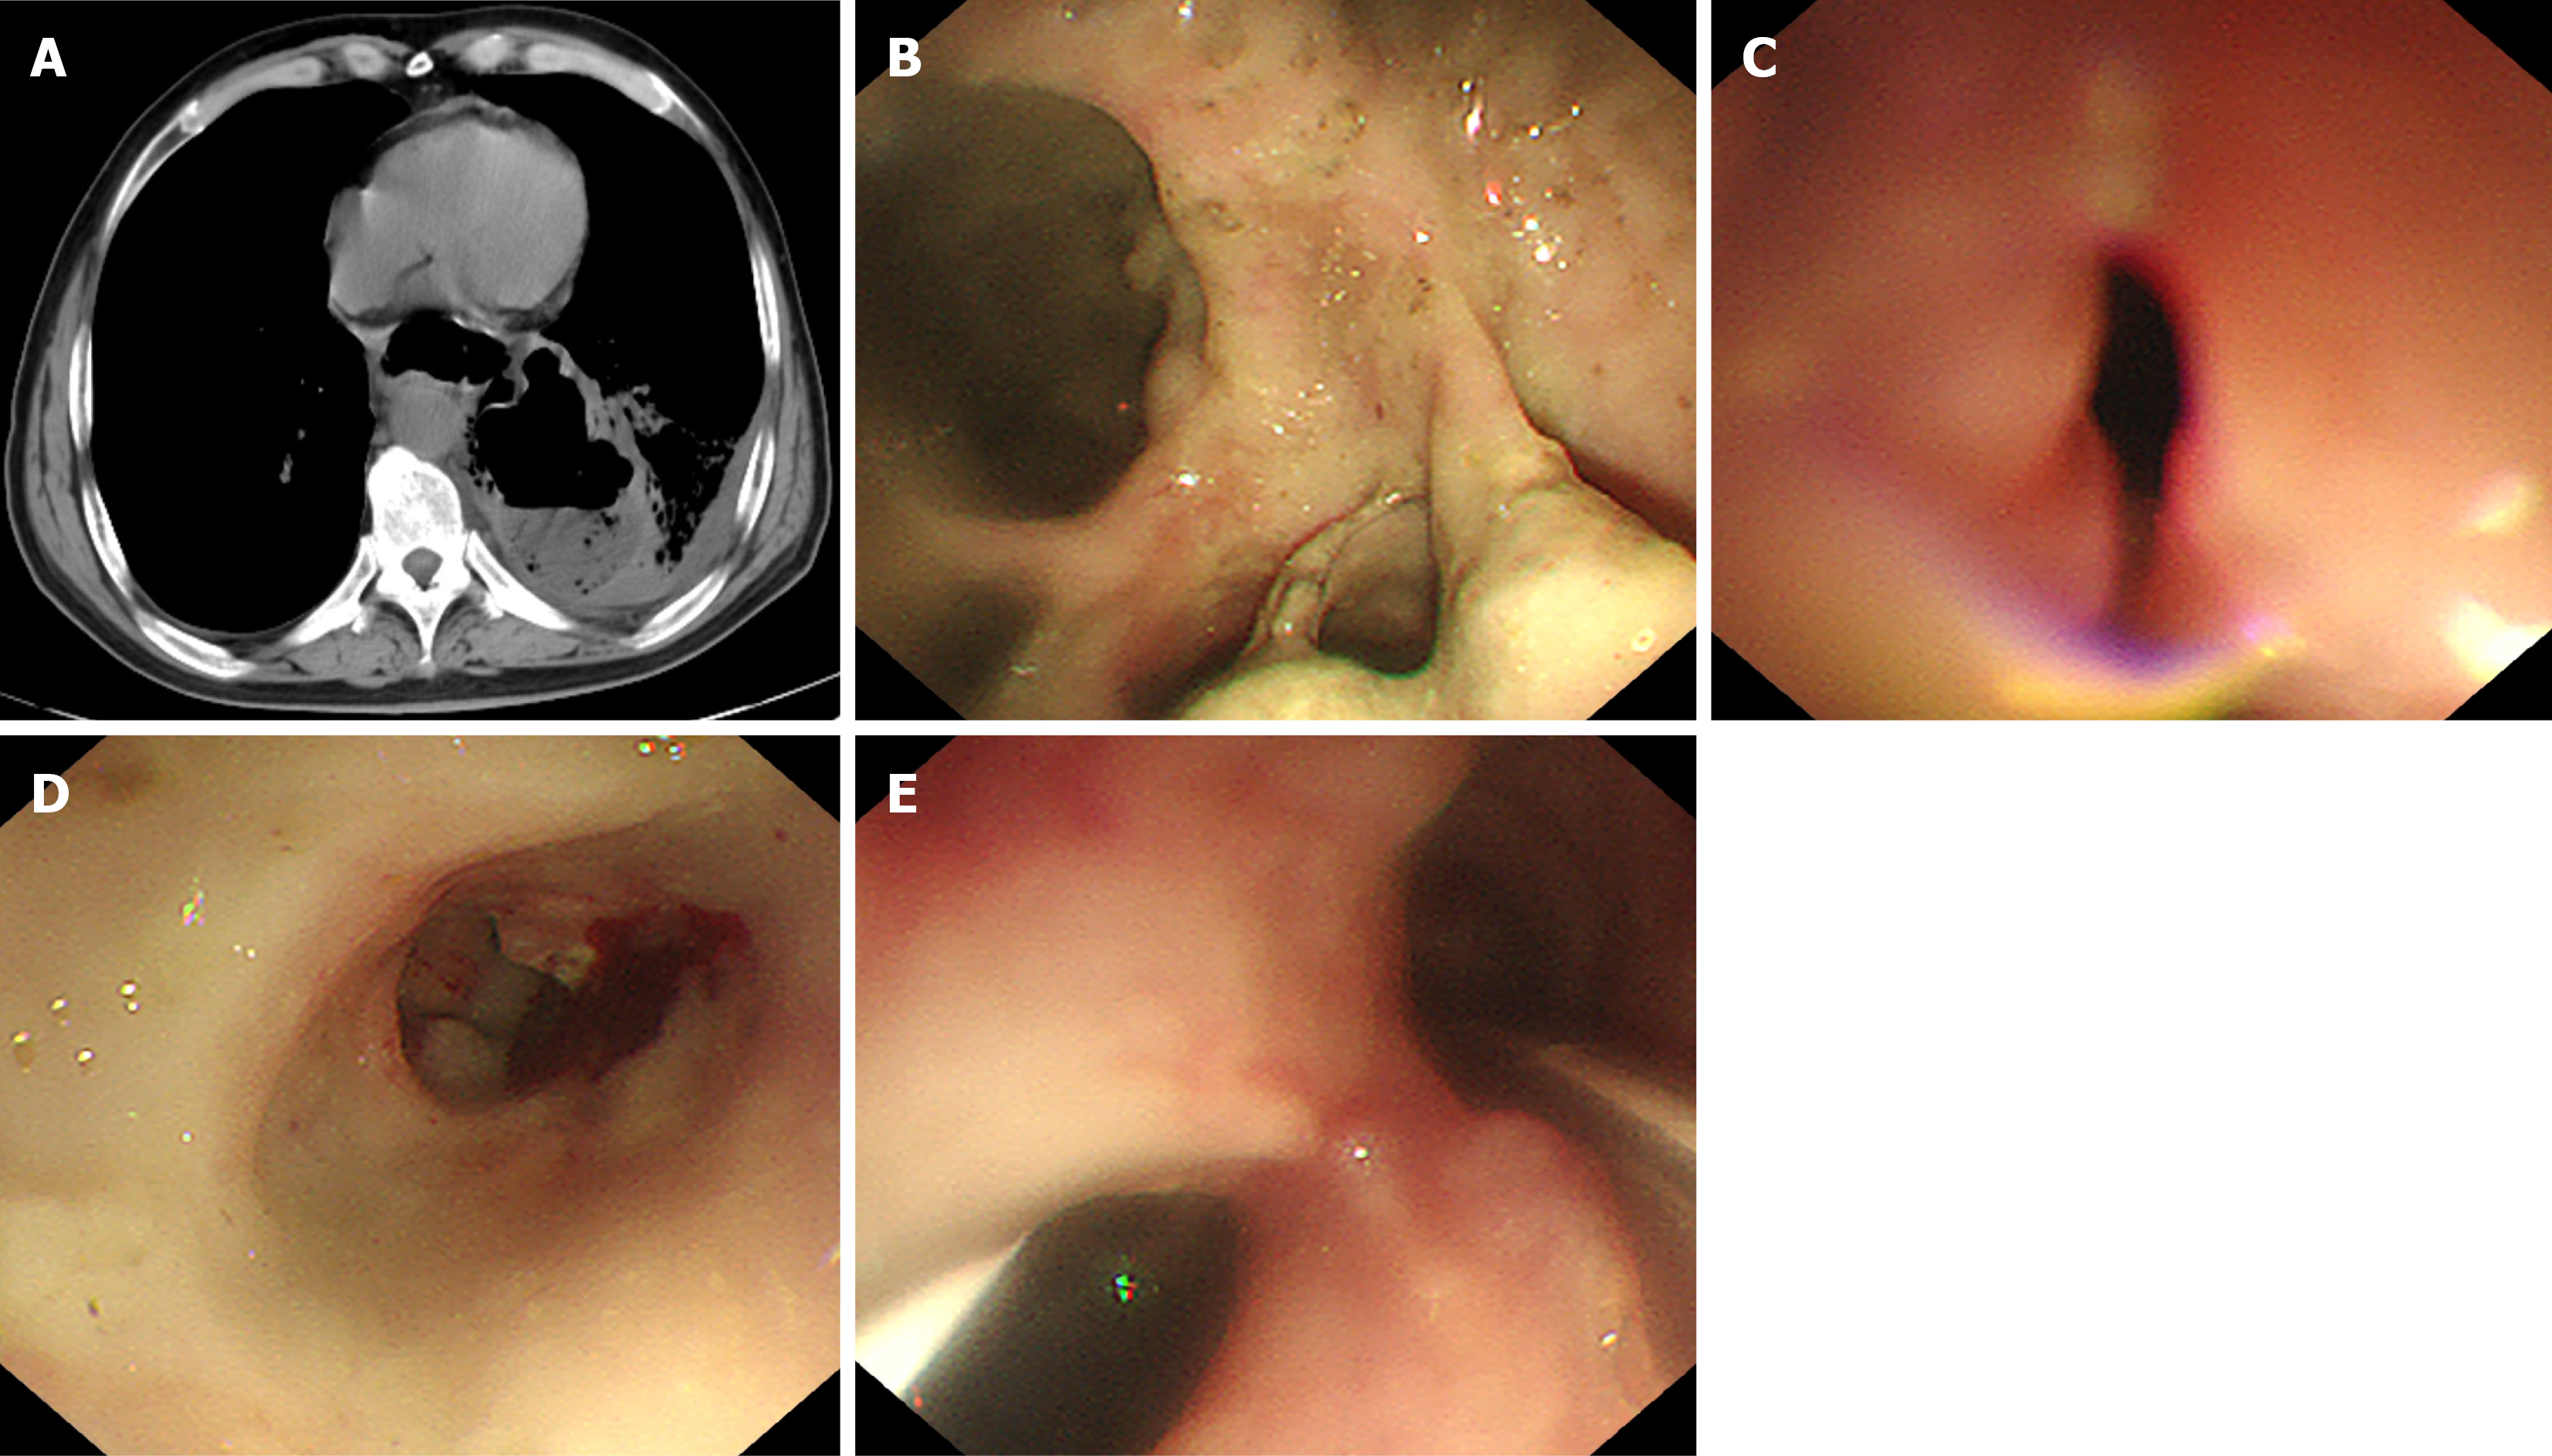
Figure 2 Chest computed tomography and follow-up gastroscopy upon clinical deterioration (December 28, 2022).
A: Chest computed tomography showing esophagomediastinal fistula and pleural effusion; B: Yellowish-white purulent secretion at the original surgical site; C: Fistula opening approximately 0.6 cm in diameter, 43 cm from nasal verge; D: Abundant yellow secretion within the sinus tract; E: Nasogastric tube placed in the sinus tract (approximately 5 cm from fistula), connected to negative suction for drainage, alongside jejunal feeding tube placed in the duodenum.
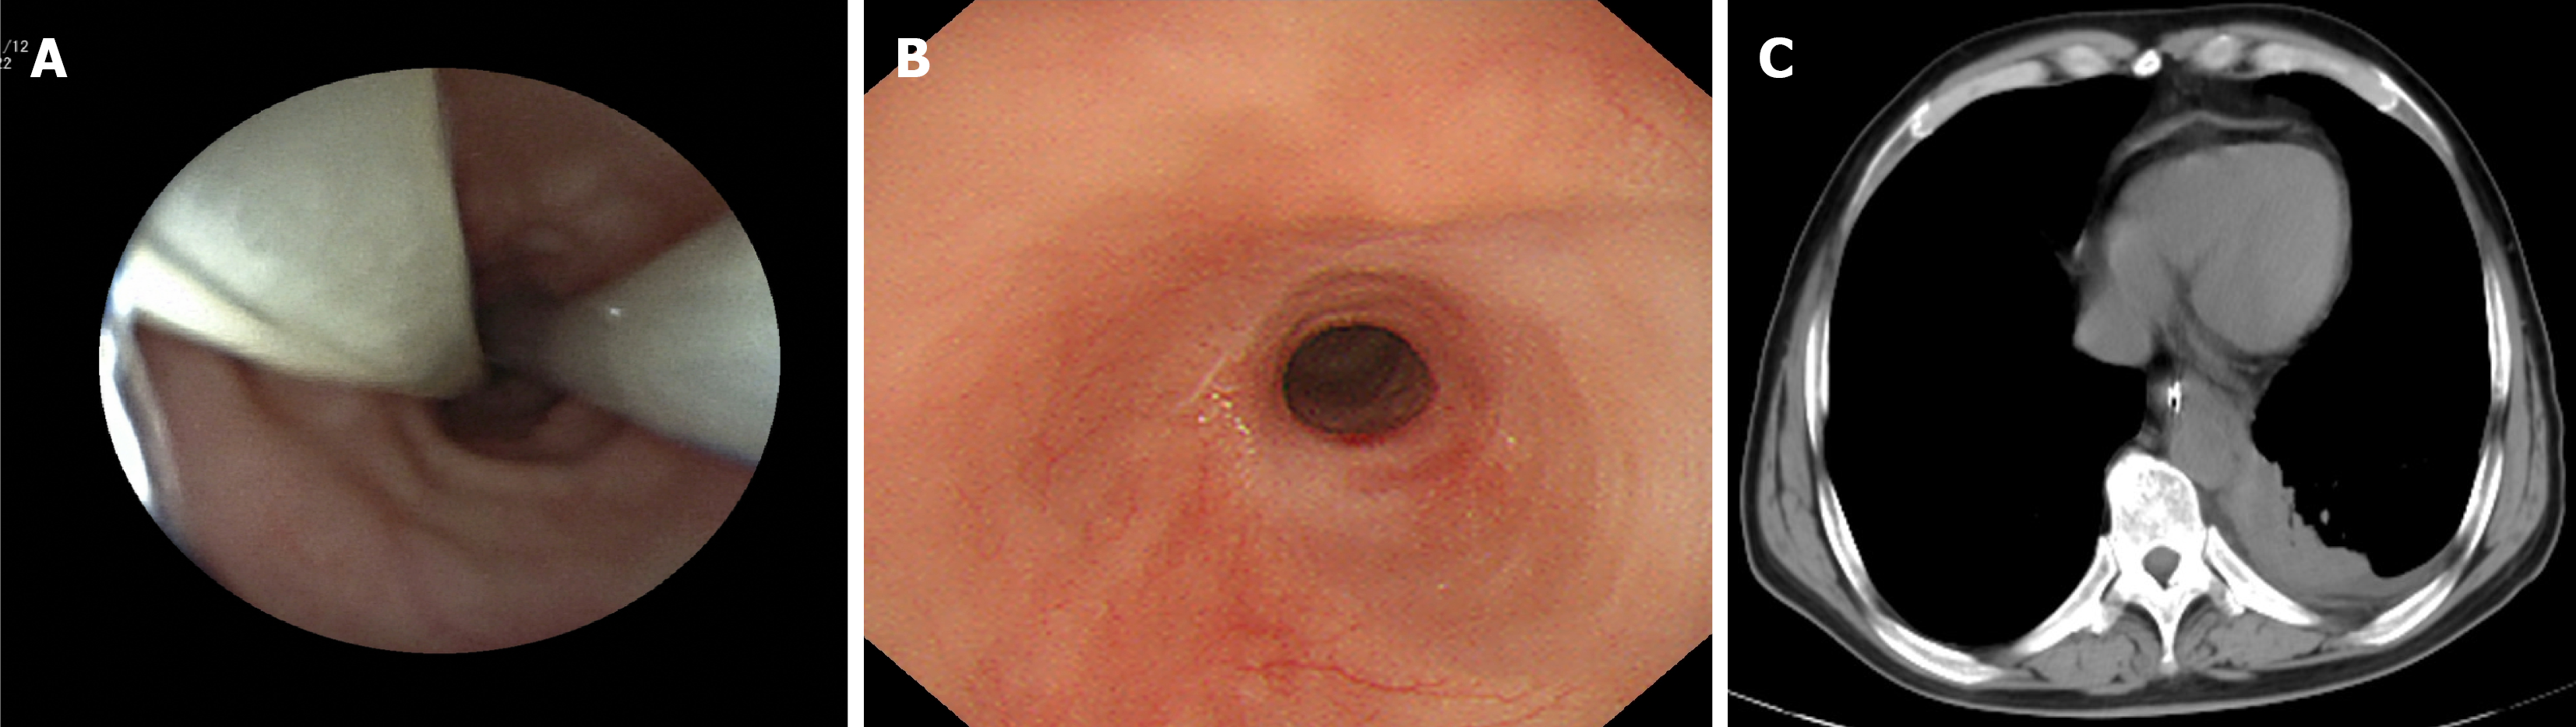
Figure 3 Follow-up examination after one week of drainage and images showing fistula healing.
A: Gastroscopy at the 2-week follow-up showing a well-positioned esophageal drainage tube; B: Gastroscopy on January 25, 2023 showing scar formation at the fistula site, confirming healing; C: Repeat chest computed tomography showing no significant effusion or pneumothorax, with pleural effusion largely absorbed.
- Citation: Ding WJ, Tang HZ, Zhou XR, Liu WH, Xu GR. Conservative management of a delayed esophagomediastinal fistula after endoscopic submucosal dissection: A case report. World J Gastrointest Surg 2026; 18(10): 122861
- URL: https://www.wjgnet.com/1948-9366/full/v18/i10/122861.htm
- DOI: https://dx.doi.org/10.4240/wjgs.122861